
Prostate anatomy · Urinary and ejaculatory pathway · Updated August 26, 2026
What Is the Prostatic Urethra? Location, Function and Bladder Outlet Obstruction
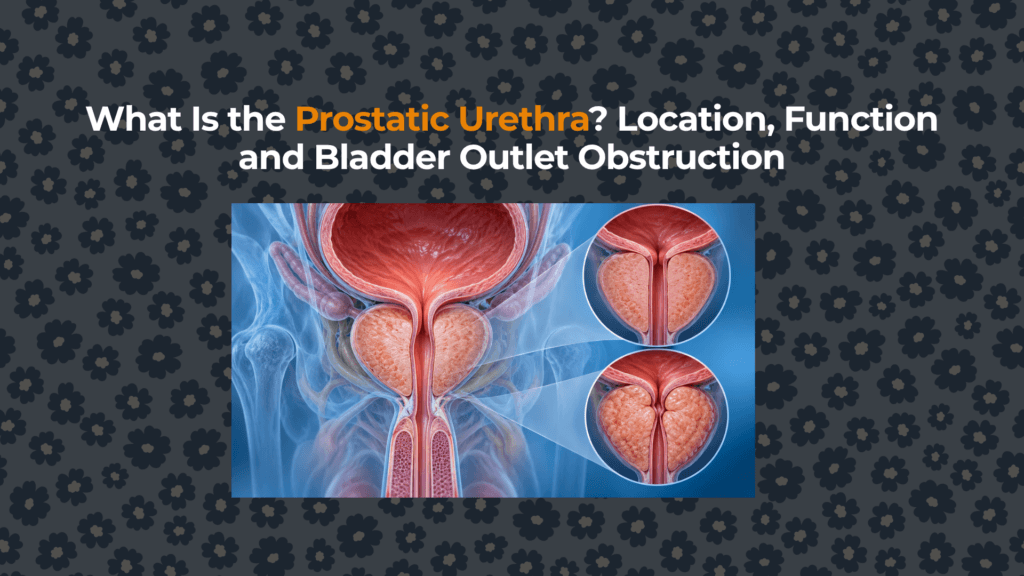
The prostatic urethra is the section of the male urethra that passes through the prostate. It is simultaneously a urine conduit, the receiving channel for prostate and ejaculatory-duct secretions, and the segment most directly affected when prostate tissue changes bladder-outlet geometry.
Where does the prostatic urethra begin and end?
The segment begins at the internal urethral opening at the bladder neck. It descends through the prostate from base to apex, then becomes the short membranous urethra as it approaches the pelvic floor and external sphincter. It is part of the posterior urethra, not the penile urethra.
The spatial sequence is clearer after reviewing the prostate’s relationship to the bladder and pelvic floor. Farther downstream, the urethra enters the corpus spongiosum and continues through the penis, as mapped in the full male urethral pathway.
How long and wide is the prostatic urethra?
Anatomy references commonly describe a length near 3–4 cm, with approximately 3.5 cm frequently cited. Individual length, angle and caliber vary with prostate shape, volume, age, bladder filling and measurement method. A cast study of 33 prostatectomy specimens reported a mean prostate urethral angle of 127.6° and a mean verumontanum-to-sphincter distance of 1.2 cm.
Those data describe a selected ex-vivo surgical sample, not a normal-population reference interval. The urethra is also a compliant, nonuniform channel rather than a rigid circular pipe, so one diameter cannot capture its functional geometry.
What structures open into the prostatic urethra?
Prostatic ducts
Numerous small ducts deliver prostate secretions into recesses alongside the urethral crest. These secretions mix with sperm and seminal-vesicle fluid during ejaculation.
Verumontanum and ejaculatory ducts
The verumontanum is a mucosal elevation on the posterior wall of the mid-prostatic urethra. The paired ejaculatory ducts open near it, lateral to the small prostatic utricle. This arrangement connects the seminal vesicles and ejaculatory pathway to the common urethral outlet.
Prostatic utricle
The prostatic utricle is a small blind-ending midline pouch. It is usually clinically inconspicuous, although enlargement, cysts or associated developmental abnormalities can occasionally matter.
How does the same channel carry urine and semen?
During urination, bladder contraction and outlet relaxation move urine through the prostatic urethra. During ejaculation, emission delivers prostatic and seminal-vesicle secretions into the posterior urethra, and coordinated muscular contractions propel semen distally.
The bladder-neck smooth-muscle mechanism helps limit retrograde flow into the bladder during ejaculation. The external sphincter complex provides voluntary urinary control and extends around the distal prostatic/membranous region more continuously than simplified diagrams suggest. Urination and ejaculation are therefore coordinated states, not simultaneous open-flow events.
How does BPH obstruct the prostatic urethra?
Transition-zone BPH can compress the urethra from the sides, elongate it, change its angle or distort the bladder outlet. A median-lobe configuration near the bladder neck can create substantial distortion even when total volume is modest.
Fluid mechanics helps explain why configuration matters: bending or creating a narrow noncircular segment can increase resistance more than a uniform reduction in diameter. Smooth-muscle tone also adds a dynamic component that can change without tissue volume changing.
| Mechanism | Anatomical change | Possible consequence | What confirms it |
|---|---|---|---|
| Lateral compression | Transition-zone tissue presses inward | Reduced caliber, higher resistance | Symptoms plus flow/residual/imaging context |
| Median-lobe distortion | Tissue protrudes toward bladder neck | Ball-valve or angulation effect | Ultrasound or cystoscopic anatomy |
| Dynamic smooth-muscle tone | Increased outlet contraction | Variable resistance | Clinical response and broader evaluation |
| Bladder compensation | Detrusor thickening/greater pressure | Temporary flow maintenance | Imaging or pressure-flow studies when indicated |
| Bladder decompensation | Reduced contractility after chronic load or other disease | Residual urine/retention | Residual measurement and selected urodynamics |
How is the prostatic urethra examined?
Ultrasound and MRI show its course indirectly and demonstrate surrounding prostate morphology. Cystoscopy views the lumen directly and can identify narrowing, median-lobe obstruction, stones, bleeding sources or other structural findings. Uroflowmetry measures the resulting urine-flow pattern, while post-void residual assesses emptying. Pressure-flow urodynamics can distinguish outlet resistance from impaired bladder contractility in selected uncertain cases.
No single test answers every question. The future BPH diagnostic pathway links symptoms, examination, PSA context, urinalysis, flow and residual urine without equating one abnormal result with one diagnosis.
Prostatic vs membranous vs penile urethra
| Segment | Approximate location | Key surrounding tissue | Main significance |
|---|---|---|---|
| Prostatic | Bladder neck through prostate | Prostate zones and sphincter components | Receives prostatic/ejaculatory ducts; affected by BPH |
| Membranous | Prostate apex through perineal membrane | External urethral sphincter | Short, relatively fixed continence-critical segment |
| Spongy/penile | Bulb through penile shaft to meatus | Corpus spongiosum | Final urine and semen conduit |
In the penis, the low-pressure corpus spongiosum protects urethral patency while the paired corpora cavernosa become rigid.
Summary
The prostatic urethra is a roughly 3–4 cm posterior-urethral segment extending from bladder neck to prostate apex. It carries urine, receives prostate and ejaculatory-duct secretions near the verumontanum and transitions toward the continence-critical membranous urethra. BPH can compress or distort it, but symptoms reflect the combined behavior of prostate tissue, urethral geometry, sphincters and bladder muscle. Diagnosis therefore requires more than prostate size or symptom description alone.
This page provides medical education and cannot diagnose urinary obstruction.


