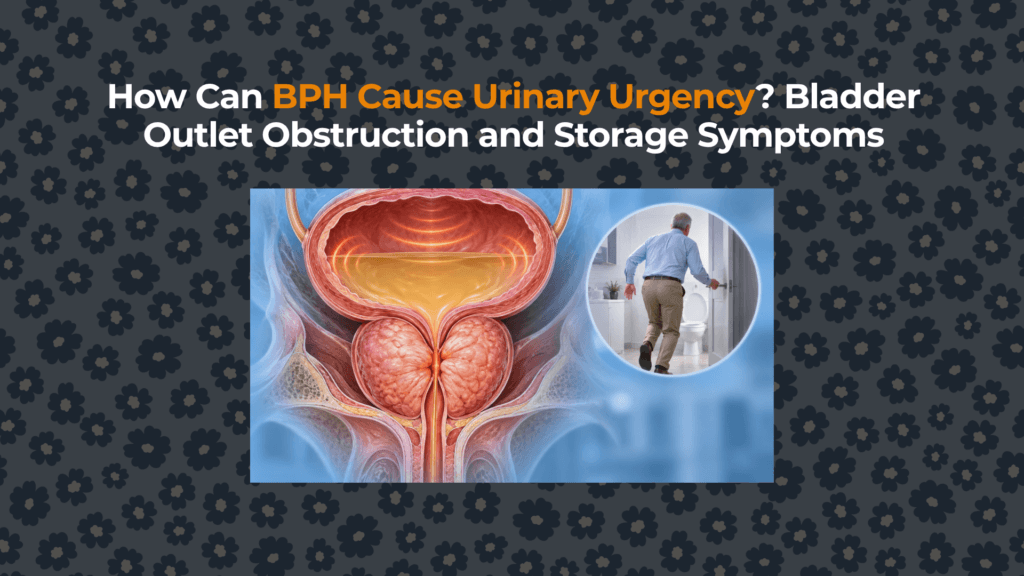
BPH can contribute to urgency through outlet-related bladder changes; urgency is a difficult-to-defer need to urinate and does not prove prostate obstruction.

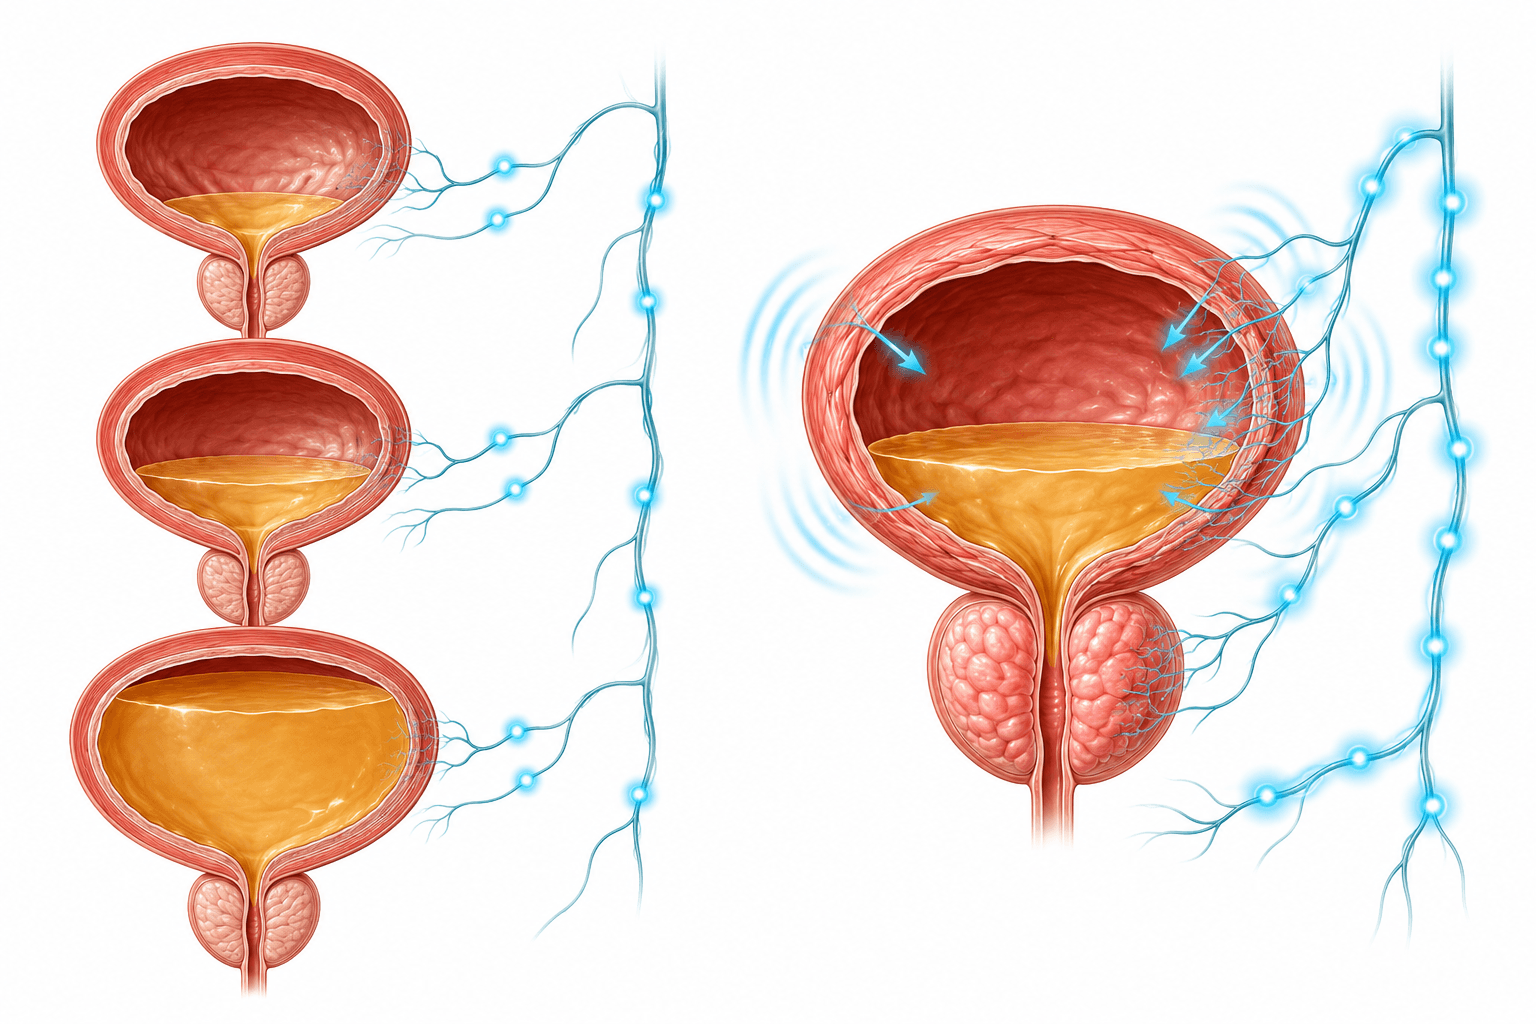
Normal filling sensation rises gradually; urgency behaves differently
BPH-associated urgency is a difficult-to-defer need to urinate; altered bladder sensation or involuntary contractions can contribute without proving prostate obstruction. Urgency is a difficult-to-defer signal that can occur at a lower-than-expected volume. It may reflect bladder oversensitivity without a measurable contraction, or coexist with detrusor overactivity.
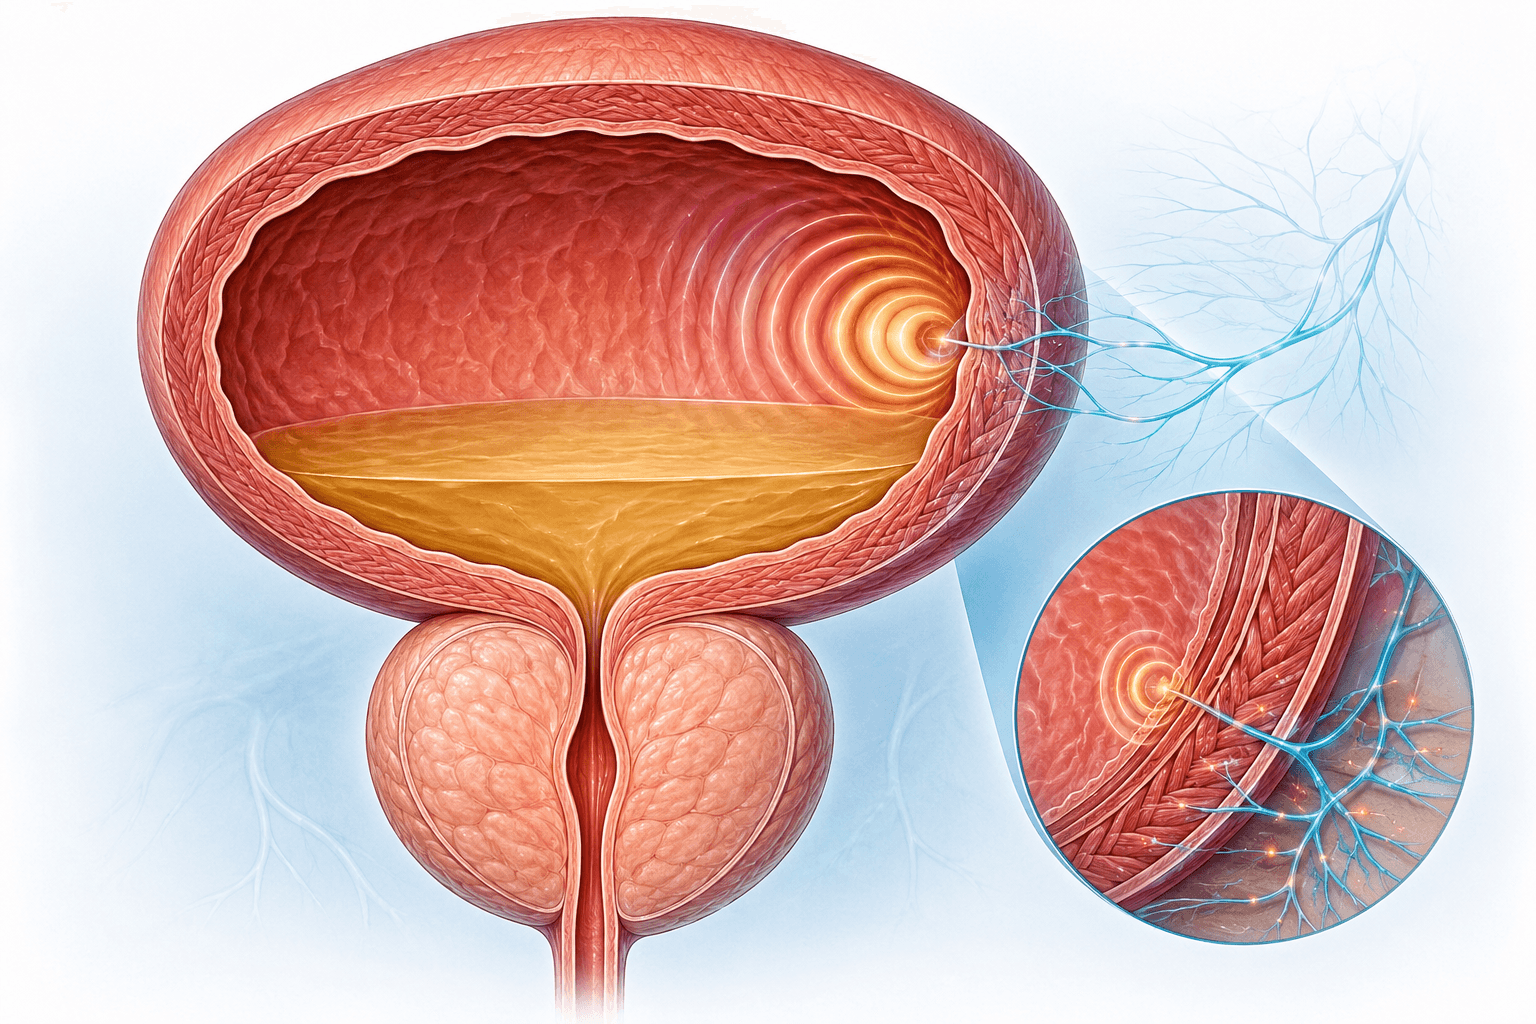
How can an enlarged prostate influence bladder signaling?
BPH can influence urgency indirectly through outlet resistance, residual urine and changes in bladder function rather than through prostate size alone. The relationship is therefore indirect and variable. The BPH hub distinguishes histologic growth from enlargement and functional obstruction.
| Proposed pathway | Biological change | Clinical expression | What it does not prove |
|---|---|---|---|
| Pressure load | Detrusor works against outlet resistance | Wall remodeling; altered storage | That every enlarged gland obstructs |
| Afferent amplification | Filling signals may be perceived earlier | Difficult-to-defer urge at lower volume | A detrusor contraction |
| Detrusor overactivity | Involuntary pressure rise during filling | Urgency with or without leakage | That BPH caused the contraction |
| Residual urine | Less usable capacity remains after voiding | Earlier refill threshold | Obstruction rather than weak contraction |
Urgency, frequency and detrusor overactivity are not interchangeable
BPH-associated urgency describes a sensation, frequency describes voiding count, and detrusor overactivity describes contractions measured during testing.
| Term | Type | Meaning | How established |
|---|---|---|---|
| Urgency | Symptom | Sudden compelling desire to void that is difficult to defer | Patient report |
| Frequency | Symptom | Voiding more often than considered normal | Report + diary |
| Urgency urinary incontinence | Symptom | Leakage accompanied or immediately preceded by urgency | Patient report/diary |
| Overactive bladder | Symptom syndrome | Urgency, usually with frequency/nocturia, with or without urgency incontinence, absent obvious pathology | Clinical evaluation |
| Detrusor overactivity | Urodynamic observation | Involuntary detrusor contraction during filling | Cystometry |
Which findings support a prostate contribution?
Prostate-linked urgency is more plausible with impaired flow, residual urine or outlet abnormalities, while storage severity alone cannot establish obstruction. Yet storage severity correlates imperfectly with obstruction. The preceding frequency article shows how a diary separates count from volume; the weak-stream page explains objective flow limits.
What evaluation goes beyond the prostate?
Urgency evaluation in men with BPH also assesses infection, intake, medicines, urine production, bladder storage and neurologic or systemic causes.
| Evidence layer | Question answered | Boundary |
|---|---|---|
| History + medication review | Onset, triggers, pain, intake, neurologic/systemic context | Symptoms overlap across causes |
| Urinalysis/culture when indicated | Infection, blood or metabolic clues | A normal result does not prove BPH |
| Three-day bladder diary | Timing, volume, urgency and leakage pattern | Cannot measure outlet pressure |
| PVR + uroflow | Emptying and flow performance | Do not separate obstruction from weak contraction alone |
| Urodynamics | Detrusor overactivity, pressure–flow mechanism | Reserved for selected uncertainty |
Will treating BPH remove urgency?
BPH treatment can improve urgency when outlet resistance contributes; persistent urgency can require a separate bladder-directed assessment and treatment. Alpha blockers target dynamic tone; selected enlarged glands may benefit from 5-alpha-reductase inhibition; procedures widen the outlet. Persistent urgency can require a bladder-directed strategy. EAU guidance supports antimuscarinic or beta-3 agonist therapy for appropriate men with predominant storage LUTS, with attention to residual urine and individual risk. The related guide explains BPH and urinary hesitancy.
When is urgency urgent?
Urinary urgency with inability to void, severe bladder pain, fever or new neurologic deficits requires urgent assessment, including in men with known BPH.
Evidence synthesis
BPH can contribute to urinary urgency through outlet-related pressure load, bladder remodeling, altered afferent signaling, detrusor overactivity or reduced usable capacity from residual urine. Urgency remains a symptom—not proof of BPH, obstruction or an involuntary detrusor contraction. A diary, urinalysis, PVR, uroflow and selected urodynamics identify the dominant prostate, bladder, urethral or systemic mechanism.
Educational information only. Individual diagnosis and treatment require qualified clinical assessment.
Watch: BPH urinary symptoms
BPH can contribute to urgency through outlet-related bladder changes; urgency is a difficult-to-defer need to urinate and does not prove prostate obstruction. FactBasedUrology explains weak stream, urgency and nocturia in this educational video.