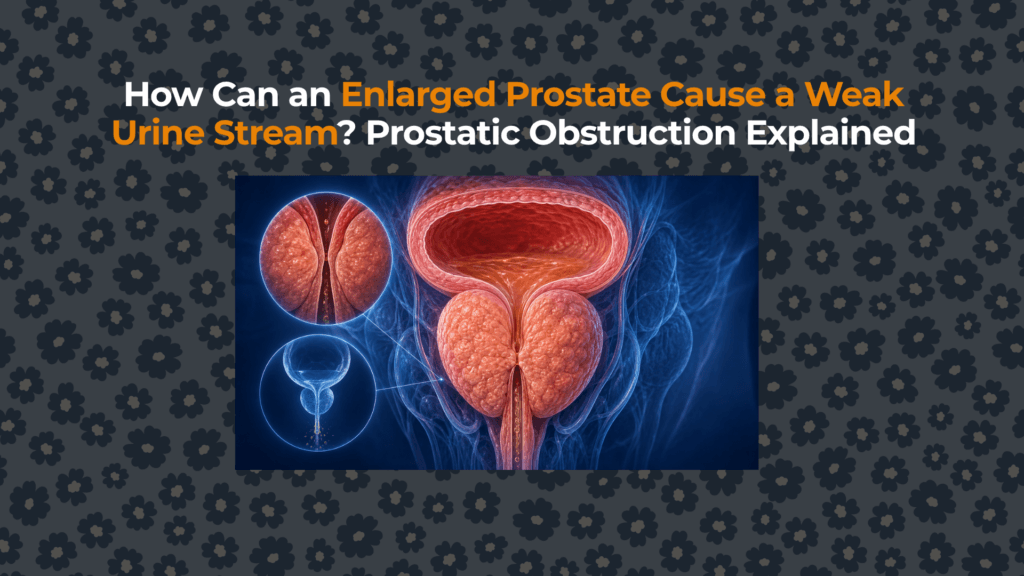
An enlarged prostate can weaken urine flow by increasing outlet resistance; bladder contraction, urethral narrowing and voided volume also influence stream strength.

From prostate growth to reduced flow: the causal chain
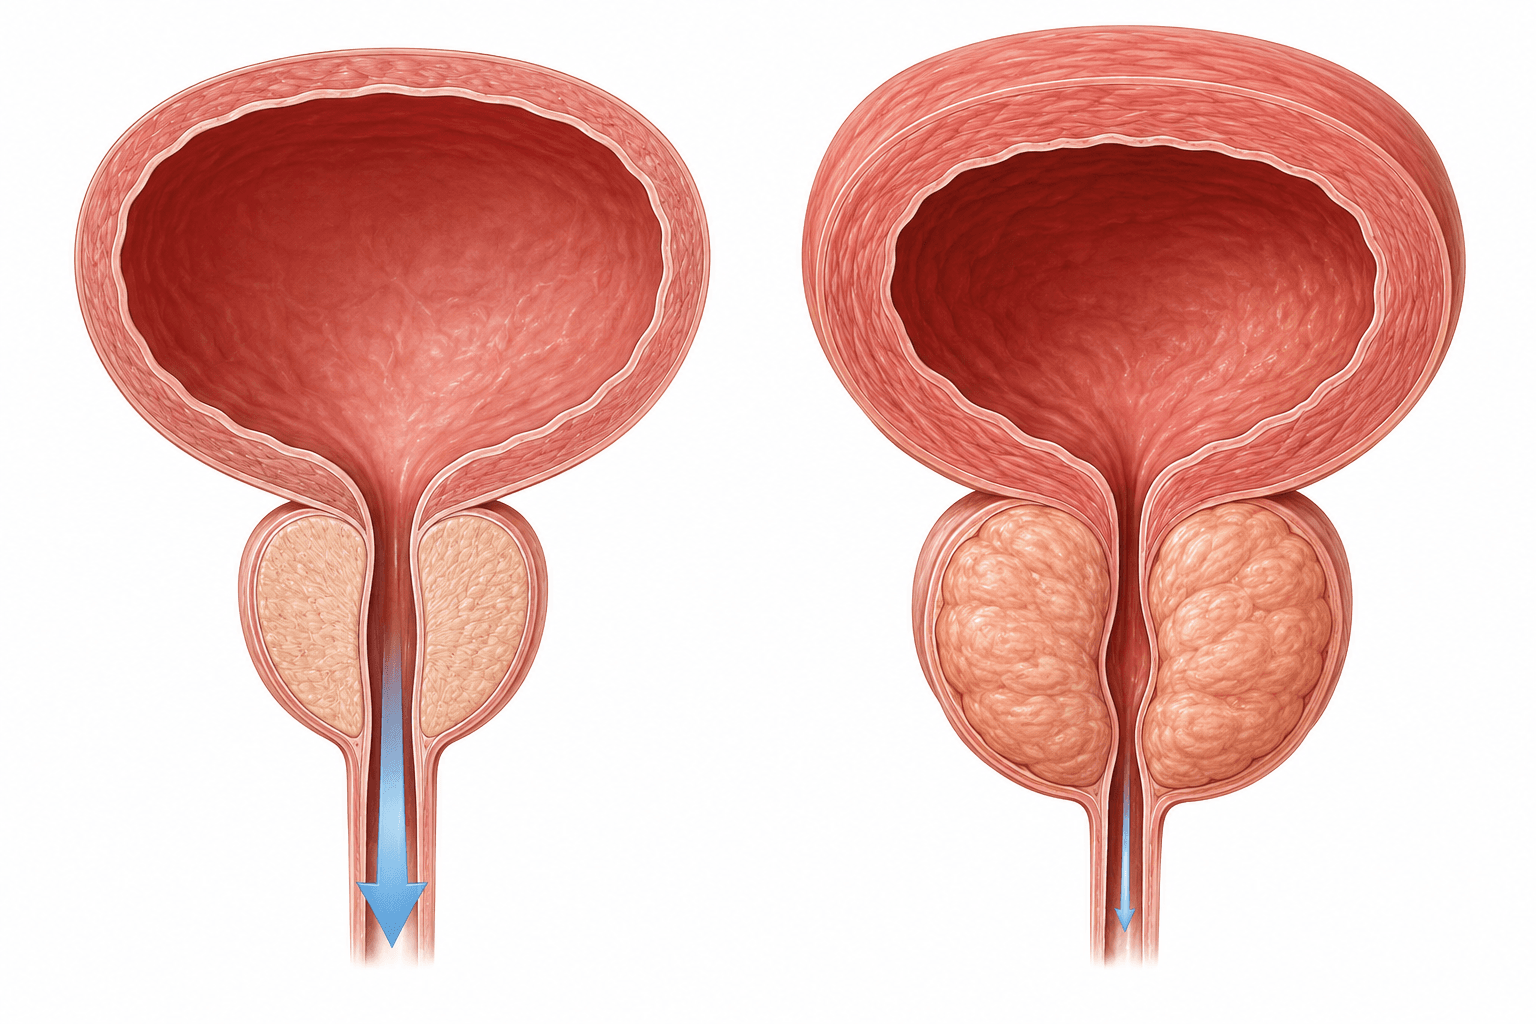
An enlarged prostate can weaken urine flow by narrowing or deforming the outlet and increasing smooth-muscle resistance around the urethra.
BPH begins as non-cancerous cellular growth, mainly in the transition zone around the prostatic urethra. Its clinical effect depends less on total grams of tissue than on where that tissue grows, the geometry of the bladder outlet and the tone of local smooth muscle.
Static and dynamic resistance are different
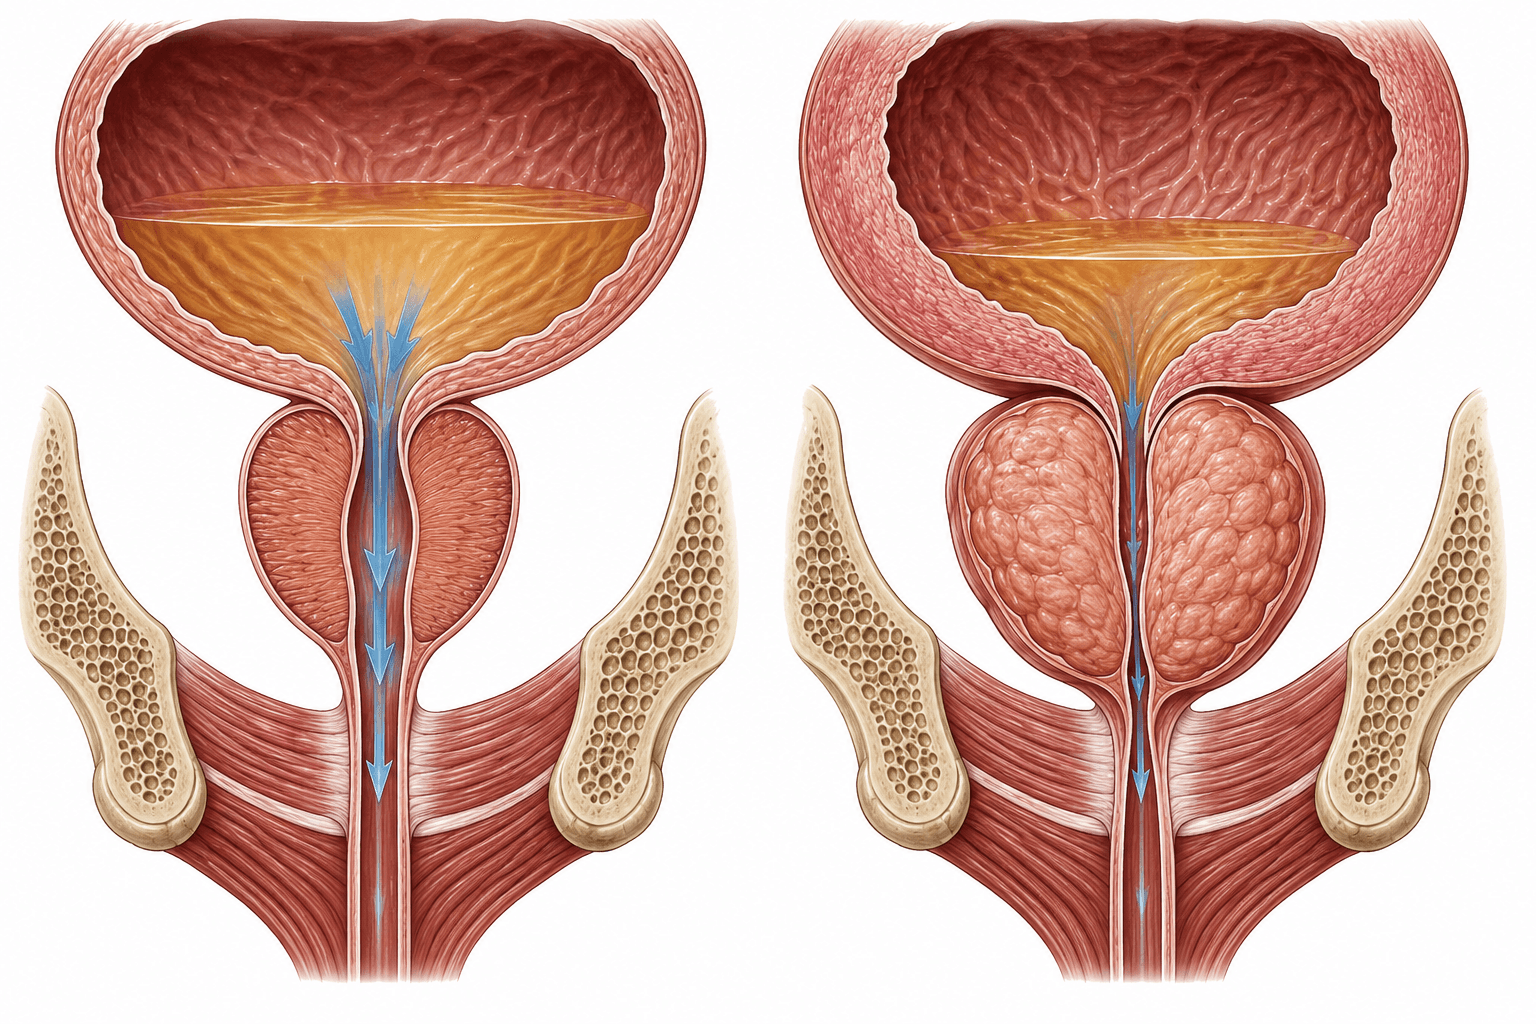
Enlarged-prostate static resistance comes from tissue geometry; dynamic resistance comes from muscle tone, and the two components respond to different treatments.
| Component | Mechanism | What can modify it | What it does not establish |
|---|---|---|---|
| Static | Tissue bulk, median-lobe protrusion and outlet geometry reduce the effective lumen | 5-alpha-reductase inhibitors over months; tissue-removing or channel-widening procedures | A large gland is not automatically obstructed |
| Dynamic | Alpha-adrenergic smooth-muscle tone in prostate and bladder neck raises resistance | Alpha blockers can relax tone relatively quickly | Symptom improvement does not measure gland shrinkage |
| Bladder response | Detrusor pressure rises to preserve emptying against resistance | Duration of obstruction, age, neurologic and metabolic health | High pressure cannot be inferred from stream appearance |
Why the bladder can hide obstruction—until it cannot
The bladder can initially compensate for enlarged-prostate resistance by generating more pressure; later weak contraction can coexist with obstruction. Over time, remodeling may include increased wall thickness and altered compliance. Some bladders later contract less effectively, so obstruction and detrusor underactivity may coexist. This is why a man can have a modestly enlarged prostate with major difficulty, or a large prostate with little difficulty; NIDDK explicitly notes that symptom severity is not directly determined by prostate size.
What does a “weak stream” mean on testing?
Weak stream testing measures urine flow over time; uroflowmetry reports maximum flow, voided volume and curve shape without independently diagnosing prostate obstruction. Uroflowmetry records urine volume against time and reports maximum flow (Qmax), average flow, voided volume and curve shape. The EAU recommends interpreting these together and obtaining a voided volume above 150 mL when possible; a low-volume void can look falsely weak. Abnormal or unrepresentative tests often need repeating.
Thresholds change sensitivity and specificity
Weak-stream Qmax thresholds trade sensitivity against specificity for obstruction; a low value raises suspicion but does not establish an enlarged-prostate cause.
| EAU-reported Qmax threshold | Sensitivity for BOO | Specificity | PPV | Interpretation |
|---|---|---|---|---|
| 10 mL/s | 47% | 70% | 70% | More specific, but misses many obstructed men |
| 15 mL/s | 82% | 38% | 67% | More sensitive, but many low results are not obstruction |
Even Qmax above 15 mL/s does not exclude obstruction because the bladder may compensate with higher pressure. Conversely, low Qmax does not prove obstruction.
One weak stream, several possible mechanisms
A weak stream can reflect prostate obstruction, weak bladder contraction, urethral narrowing, pelvic-floor dysfunction or an unrepresentative low-volume void.
| Mechanism | Pressure–flow logic | Clues that may redirect testing | How it is distinguished |
|---|---|---|---|
| Benign prostatic obstruction | Higher detrusor pressure with reduced flow | Age-associated LUTS, enlarged/reshaped outlet, intravesical protrusion | Clinical assessment; pressure–flow if uncertainty matters |
| Detrusor underactivity | Low pressure and low flow | Diabetes, neurologic disease, longstanding retention, large residual | Pressure–flow study—not flow rate alone |
| Urethral stricture | Resistance lies distal to the prostate | Prior instrumentation, trauma, infection; spraying or progressive narrowing | Cystoscopy or urethral imaging when indicated |
| Underfilled bladder/test artifact | Too little driving volume for representative flow | Voided volume below 150 mL or atypical test void | Repeat uroflow at representative volume |
| Medicines/neurologic dysfunction | Outlet tone or bladder activation changes | New drug exposure, sensory/motor symptoms | Medication and neurologic review; targeted testing |
How clinicians test whether the prostate is actually obstructing flow
Clinicians investigate enlarged-prostate weak flow with history, urine testing, uroflowmetry, residual urine and selected anatomical or pressure-flow assessment. Symptom scores measure burden, not mechanism. Uroflowmetry adds an objective flow trace; post-void residual (PVR) estimates what remains. A PVR of 50 mL has limited accuracy for obstruction in EAU data (PPV 63%, NPV 52%), because residual urine can result from obstruction or poor detrusor function.
Prostate imaging can show volume and configuration. Intravesical prostatic protrusion may add predictive information, but anatomy still does not directly measure voiding pressure. Cystoscopy evaluates the lumen when stricture, bleeding or anatomy matters.
Pressure–flow testing separates resistance from weak power
Pressure-flow testing distinguishes prostate-outlet resistance from weak bladder contraction by measuring detrusor pressure and urine flow together. The EAU defines the bladder outlet obstruction index (BOOI) as pdetQmax − 2 × Qmax: above 40 is obstructed, 20–40 equivocal and below 20 unobstructed. The bladder contractility index (BCI) is pdetQmax + 5 × Qmax; below 100 indicates weak contractility. These indices require properly measured invasive pressures and are not home calculations.
Would BPH treatment strengthen the stream?
BPH treatment can strengthen a weak stream when prostate-outlet resistance contributes; improvement is less predictable when weak bladder contraction or another cause dominates. Alpha blockers reduce dynamic smooth-muscle tone. 5-alpha-reductase inhibitors gradually reduce progression risk and prostate volume in appropriately selected enlarged glands. Procedures remove tissue or widen the channel. Improvement after treatment supports a reversible outlet component, but response varies when bladder underactivity or another lesion coexists. The distinction between histologic BPH, enlargement and measured obstruction is developed in BPH versus benign prostatic obstruction.
When is weak flow urgent?
Weak flow requires urgent care when no urine passes or severe bladder pain, fever or other acute warning signs develop; prostate enlargement does not explain these safely without assessment.
Evidence synthesis
Prostate enlargement can weaken urine flow through static tissue geometry and dynamic smooth-muscle tone at the bladder outlet. The bladder may compensate with higher pressure, so neither gland size nor stream strength alone identifies obstruction. Uroflowmetry quantifies the result but cannot identify the cause; representative voided volume, curve shape and repeated measurements matter. When treatment depends on knowing the mechanism, pressure–flow testing distinguishes prostatic/outlet resistance from detrusor underactivity.
Educational information only. Individual diagnosis and treatment require a qualified clinician.
Watch: BPH urinary symptoms
An enlarged prostate can weaken urine flow by increasing outlet resistance; bladder contraction, urethral narrowing and voided volume also influence stream strength. FactBasedUrology explains weak stream, urgency and nocturia in this educational video.
Evidence sources
- EAU Guidelines: Diagnostic Evaluation of Non-neurogenic Male LUTS.
- American Urological Association: BPH Guideline (2026).
- NIDDK: Enlarged Prostate (Benign Prostatic Hyperplasia).
- NIDDK: Symptoms and Causes of Urinary Retention.
- International Continence Society–aligned review: voiding dysfunction, obstruction and detrusor underactivity.