
What Is Median Lobe Prostate Enlargement? Anatomy, Obstruction and Treatment Relevance
A median lobe can be clinically important because of where it grows, not merely how much tissue it adds.
01. Median-Lobe Enlargement Is a Shape Phenotype, Not a Volume Diagnosis
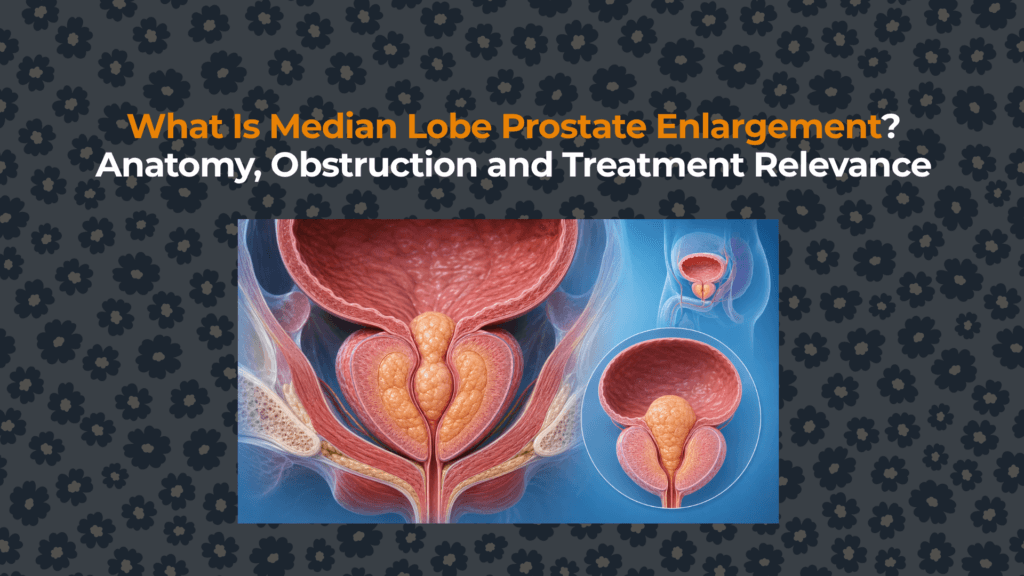
“Median lobe” is a clinical anatomical description. It does not mean the entire gland is large, and it should not be confused automatically with the prostate’s central zone. Benign nodular tissue near the bladder neck may project centrally even when lateral lobes and total volume are modest.
The prior size-versus-symptoms analysis explains why geometry can outperform volume as an individual clue.
02. Growth Toward the Bladder Creates Ball-Valve Geometry
Lateral-lobe enlargement tends to compress the prostatic urethra from the sides. A protruding median lobe can instead rise into the bladder outlet. As detrusor pressure drives urine toward the neck, the protruding tissue may distort or intermittently occlude the opening—hence the “ball-valve” analogy.
03. Intravesical Prostatic Protrusion Measures Projection, Not Tissue Type
IPP is the vertical distance from the tip of the prostate’s intravesical projection to the bladder circumference at the prostate base, commonly measured on a mid-sagittal ultrasound with adequate bladder filling. Common research grades are <5 mm, 5–10 mm and >10 mm.
IPP can arise from median and/or lateral tissue projecting into the bladder. It describes shape, not histology, cancer status or the complete cause of urinary symptoms. Measurement varies with bladder volume, imaging plane and operator technique.
04. IPP Above 10 mm Raises Obstruction Probability but Is Not Proof
The EAU guideline’s systematic-review summary reports that IPP above 10 mm had sensitivity of 0.71 and specificity of 0.77 for urodynamically determined bladder outlet obstruction. A 2026 diagnostic meta-analysis using study thresholds around 10–12 mm reported a similar pooled sensitivity of 71%.
These values mean high-grade IPP changes probability while still producing false positives and false negatives. Pressure–flow urodynamics most directly classifies outlet resistance when confirmation would change an invasive decision.
05. Symptoms, Flow and Residual Urine May Still Be Discordant
Median-lobe geometry can contribute to hesitancy, intermittent or weak flow, straining and incomplete emptying. Bladder adaptation may add urgency, frequency or nocturia. Yet symptom scores do not identify the lobe, free uroflow depends on detrusor strength and voided volume, and residual urine can reflect obstruction or weak contraction.
The BPH-versus-BPO article separates tissue growth, prostate-attributed obstruction and bladder outlet obstruction.
06. Ultrasound and Cystoscopy Answer Different Anatomical Questions
| Method | Question answered | Median-lobe contribution | Limitation |
|---|---|---|---|
| Transabdominal ultrasound | Volume, residual urine, IPP | Non-invasive sagittal projection measurement | Depends on bladder filling and imaging plane |
| Transrectal ultrasound | Detailed gland dimensions and morphology | Defines prostate-base anatomy | Invasive discomfort; geometry may differ from voiding state |
| Cystoscopy | Direct lumen and bladder-neck appearance | Shows obstructing median tissue and urethral configuration | Does not measure detrusor pressure or prove functional obstruction alone |
| MRI | Zonal anatomy and tissue characterization | Shows configuration when obtained for an appropriate indication | Not routinely required only to diagnose uncomplicated LUTS |
| Pressure–flow study | Pressure required to generate flow | Classifies functional obstruction | Does not by itself map the exact lobe causing resistance |
The volume measurement article explains modality disagreement; the prostatic-urethra guide maps the affected channel.
07. Median-Lobe Anatomy Changes Medication Expectations
Alpha-blockers reduce smooth-muscle tone but do not remove protruding tissue. 5-alpha-reductase inhibitors can shrink enlarged androgen-responsive prostate tissue gradually, especially when progression risk and volume are higher. Observational studies suggest high-grade IPP may respond less well to alpha-blocker monotherapy, but anatomy alone does not determine whether medication will fail.
08. Procedure Selection Must Explicitly Account for the Median Lobe
Some procedures remove, vaporize or enucleate obstructing tissue and can directly address median-lobe anatomy. Other minimally invasive techniques have anatomy-specific eligibility, operator requirements or evidence that has evolved by device and study. A procedure appropriate for lateral-lobe compression may be unsuitable or require a modified technique when a median lobe projects into the bladder.
| Procedure principle | Median-lobe question | Other decision variables |
|---|---|---|
| Resection or vaporization | Can the protruding tissue be treated safely and completely? | Volume, bleeding risk, durability and ejaculation priorities |
| Enucleation | Does anatomy favor adenoma removal across lobes? | Gland size, expertise, anesthesia and recovery |
| Water-vapor ablation | Is the median lobe identifiable and targetable within current indications? | Volume range, retention risk, onset and retreatment evidence |
| Prostatic urethral lift | Is obstructive median-lobe treatment supported for the device, technique and anatomy? | Local expertise, guideline/device labeling and ejaculation goals |
| Other minimally invasive systems | Was obstructive median-lobe anatomy included in pivotal evidence? | Current eligibility, durability and comparative data |
09. Anatomy, Function and Patient Priorities Form the Treatment Decision
10. Precise Reporting Prevents “Large Prostate” From Hiding High-Impact Geometry
A useful report separates total prostate volume, median-lobe presence, IPP in millimetres, bladder volume during measurement, residual urine and any bladder-neck or urethral findings. Clinical notes should separately record LUTS phenotype, bother, flow and whether obstruction is suspected or demonstrated.
The BPH hub maps the broader management pathway. Continue next to intravesical prostatic protrusion for the dedicated measurement evidence.
Evidence sources
- EAU 2026 Male LUTS Guideline: IPP and diagnostic evaluation.
- AUA 2026 BPH Guideline.
- Han et al., 2026: IPP diagnostic meta-analysis.
- Clinical considerations for intravesical prostatic protrusion.
- Gharbieh et al., 2023: clinical significance of the prostatic middle lobe.
- Prostatic urethral lift evidence for obstructive median lobes.


