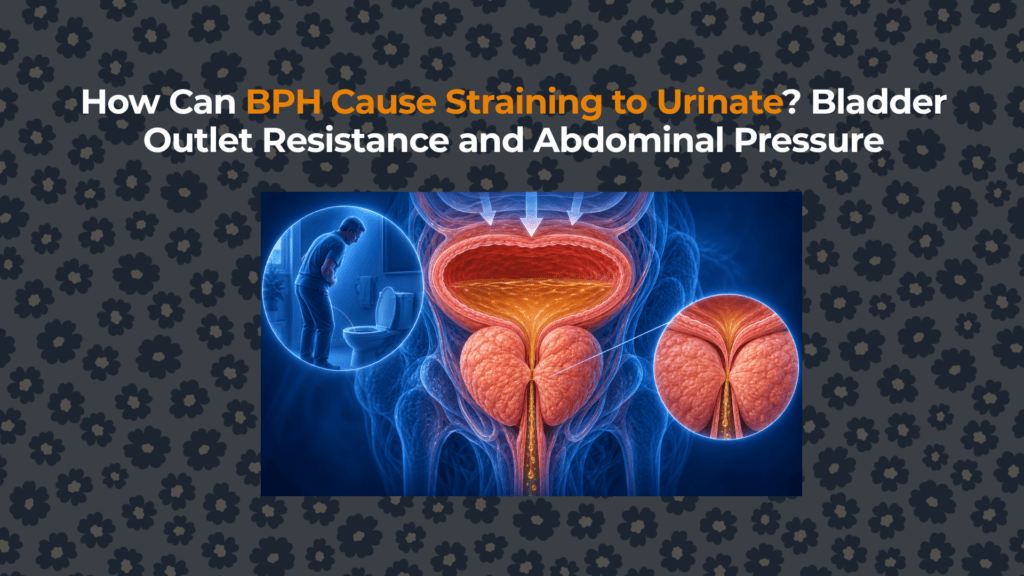
BPH can contribute to straining when outlet resistance exceeds effective bladder pressure; abdominal effort does not establish the cause.

Urination depends on a pressure budget
Straining with BPH adds abdominal effort to urination when outlet resistance or weak bladder contraction prevents an efficient stream. During efficient voiding, detrusor contraction supplies the main propulsive pressure while the sphincter, pelvic floor and bladder neck relax. Abdominal pressure is not the same measurement as bladder-muscle pressure.
How can BPH increase the need to strain?
BPH can increase straining by raising tissue-related or muscular outlet resistance beyond the pressure supplied by an effective bladder contraction. Tissue enlargement may add static resistance; alpha-adrenergic smooth-muscle tone adds a dynamic component. The bladder may initially compensate by generating greater pressure. If that is insufficient—or if contraction weakens—a person may tighten the abdomen to initiate or sustain flow. The BPH hub separates enlargement from functional obstruction.
| Mechanism | Pressure consequence | Possible behavior | What remains uncertain |
|---|---|---|---|
| Periurethral enlargement | Static outlet resistance may rise | Strain to start or maintain flow | Large prostates may cause few symptoms |
| Smooth-muscle tone | Dynamic resistance may rise | Abdominal effort supplements opening | Tone is not visible from symptoms |
| Detrusor compensation | Bladder pressure rises | Flow may occur without obvious strain | Pressure requires urodynamic measurement |
| Detrusor underactivity | Propulsive force is insufficient/brief | Strain despite little outlet obstruction | Can coexist with BPH |
Straining, hesitancy and weak stream describe different observations
BPH-associated straining describes muscular effort; hesitancy describes delayed initiation, and weak stream describes reduced perceived flow.
| Term | Core observation | Diagnostic limit |
|---|---|---|
| Straining | Intense muscular effort to initiate, maintain or improve flow | Does not identify obstruction |
| Hesitancy | Delay before flow starts | May occur with or without straining |
| Weak stream | Reduced perceived stream force | May reflect resistance or weak detrusor contraction |
| Intermittency | Flow stops and restarts | Does not locate the cause |
| Retention | Inability or incomplete ability to empty | Cannot be diagnosed by effort alone |
Why is abdominal straining not a safe obstruction test?
Straining cannot diagnose BPH obstruction because abdominal effort can compensate for weak bladder contraction, urethral narrowing or impaired outlet relaxation. A low flow rate can result from benign prostatic obstruction, urethral stricture, pelvic-floor contraction, detrusor underactivity, insufficient voided volume or a mixed mechanism. The preceding hesitancy article explains delayed initiation; the weak-stream guide explains flow-rate boundaries.
Which evidence separates resistance from weak bladder force?
Straining evaluation combines history, urinalysis, residual urine, uroflowmetry and selected pressure-flow testing to distinguish prostate resistance from bladder weakness.
| Evidence layer | What it contributes | Boundary |
|---|---|---|
| History + medicine review | Onset, effort pattern, pain, constipation, neurologic and drug context | Symptoms overlap |
| Urinalysis | Infection, blood and metabolic clues | Normal findings do not confirm BPH |
| PVR | Amount remaining after voiding | May rise with obstruction or weak contraction |
| Uroflowmetry | Qmax, voided volume and curve | Low flow is not cause-specific |
| Prostate/outlet assessment | Volume, configuration and urethral anatomy | Anatomy does not equal obstruction |
| Pressure–flow study | Separates detrusor from abdominal pressure and relates pressure to flow | Used selectively when results would change management |
Will treating BPH stop the need to strain?
BPH treatment can reduce straining when prostate-related resistance contributes; persistent effort needs reassessment for bladder weakness and other causes. Alpha blockers reduce dynamic smooth-muscle tone; 5-alpha-reductase inhibitors address progression risk in selected enlarged glands over months; procedures reduce anatomical resistance. Persistent straining after outlet treatment should prompt reassessment for detrusor underactivity, urethral narrowing, pelvic-floor dysfunction, constipation, medicines or neurologic disease. The related guide explains BPH and an intermittent urine stream.
When does straining require urgent assessment?
Straining requires urgent assessment when no urine passes, especially with bladder pain or swelling; fever or new neurologic deficits also require urgent care.
Evidence synthesis
BPH can contribute to straining when prostate-related resistance exceeds the pressure available from an efficient detrusor contraction. Abdominal effort may bridge that pressure gap, but it can also compensate for weak bladder contraction or dysfunctional outlet relaxation. History, urinalysis, PVR, uroflow and anatomy provide evidence layers; selected pressure–flow testing identifies whether resistance, detrusor force or both dominate.
Educational information only. Individual diagnosis and treatment require qualified clinical assessment.
Watch: BPH urinary symptoms
BPH can contribute to straining when outlet resistance exceeds effective bladder pressure; abdominal effort does not establish the cause. FactBasedUrology explains weak stream, urgency and nocturia in this educational video.