Prostate Health › BPH Evaluation
A digital rectal examination is a brief physical examination in which a clinician uses a gloved, lubricated finger to feel the back surface of the prostate through the rectal wall. It provides a clinical estimate of prostate size and allows the examiner to assess contour, symmetry, consistency, tenderness and palpable abnormalities.
The DRE can add useful information during the evaluation of male lower urinary tract symptoms (LUTS), but it is not a stand-alone test for benign prostatic hyperplasia, urinary obstruction or prostate cancer. Findings must be interpreted with the history, symptom assessment, urinalysis and other tests selected for the individual.
During a prostate DRE, a clinician feels the portion of the gland next to the rectum. A smooth, symmetric gland may be consistent with benign enlargement, while a hard nodule, induration, marked asymmetry or irregular contour may require further assessment. Tenderness can occur with inflammation or infection. DRE estimates are subjective: the examination cannot accurately calculate prostate volume, show how tightly the urethra is compressed, prove bladder outlet obstruction, or rule cancer in or out.
DRE is one component of the broader evaluation of BPH and male LUTS. The result helps a clinician decide whether an imaging test, PSA assessment or another targeted investigation is appropriate.
01. Prostate Exam: How It Is Performed and Interpreted
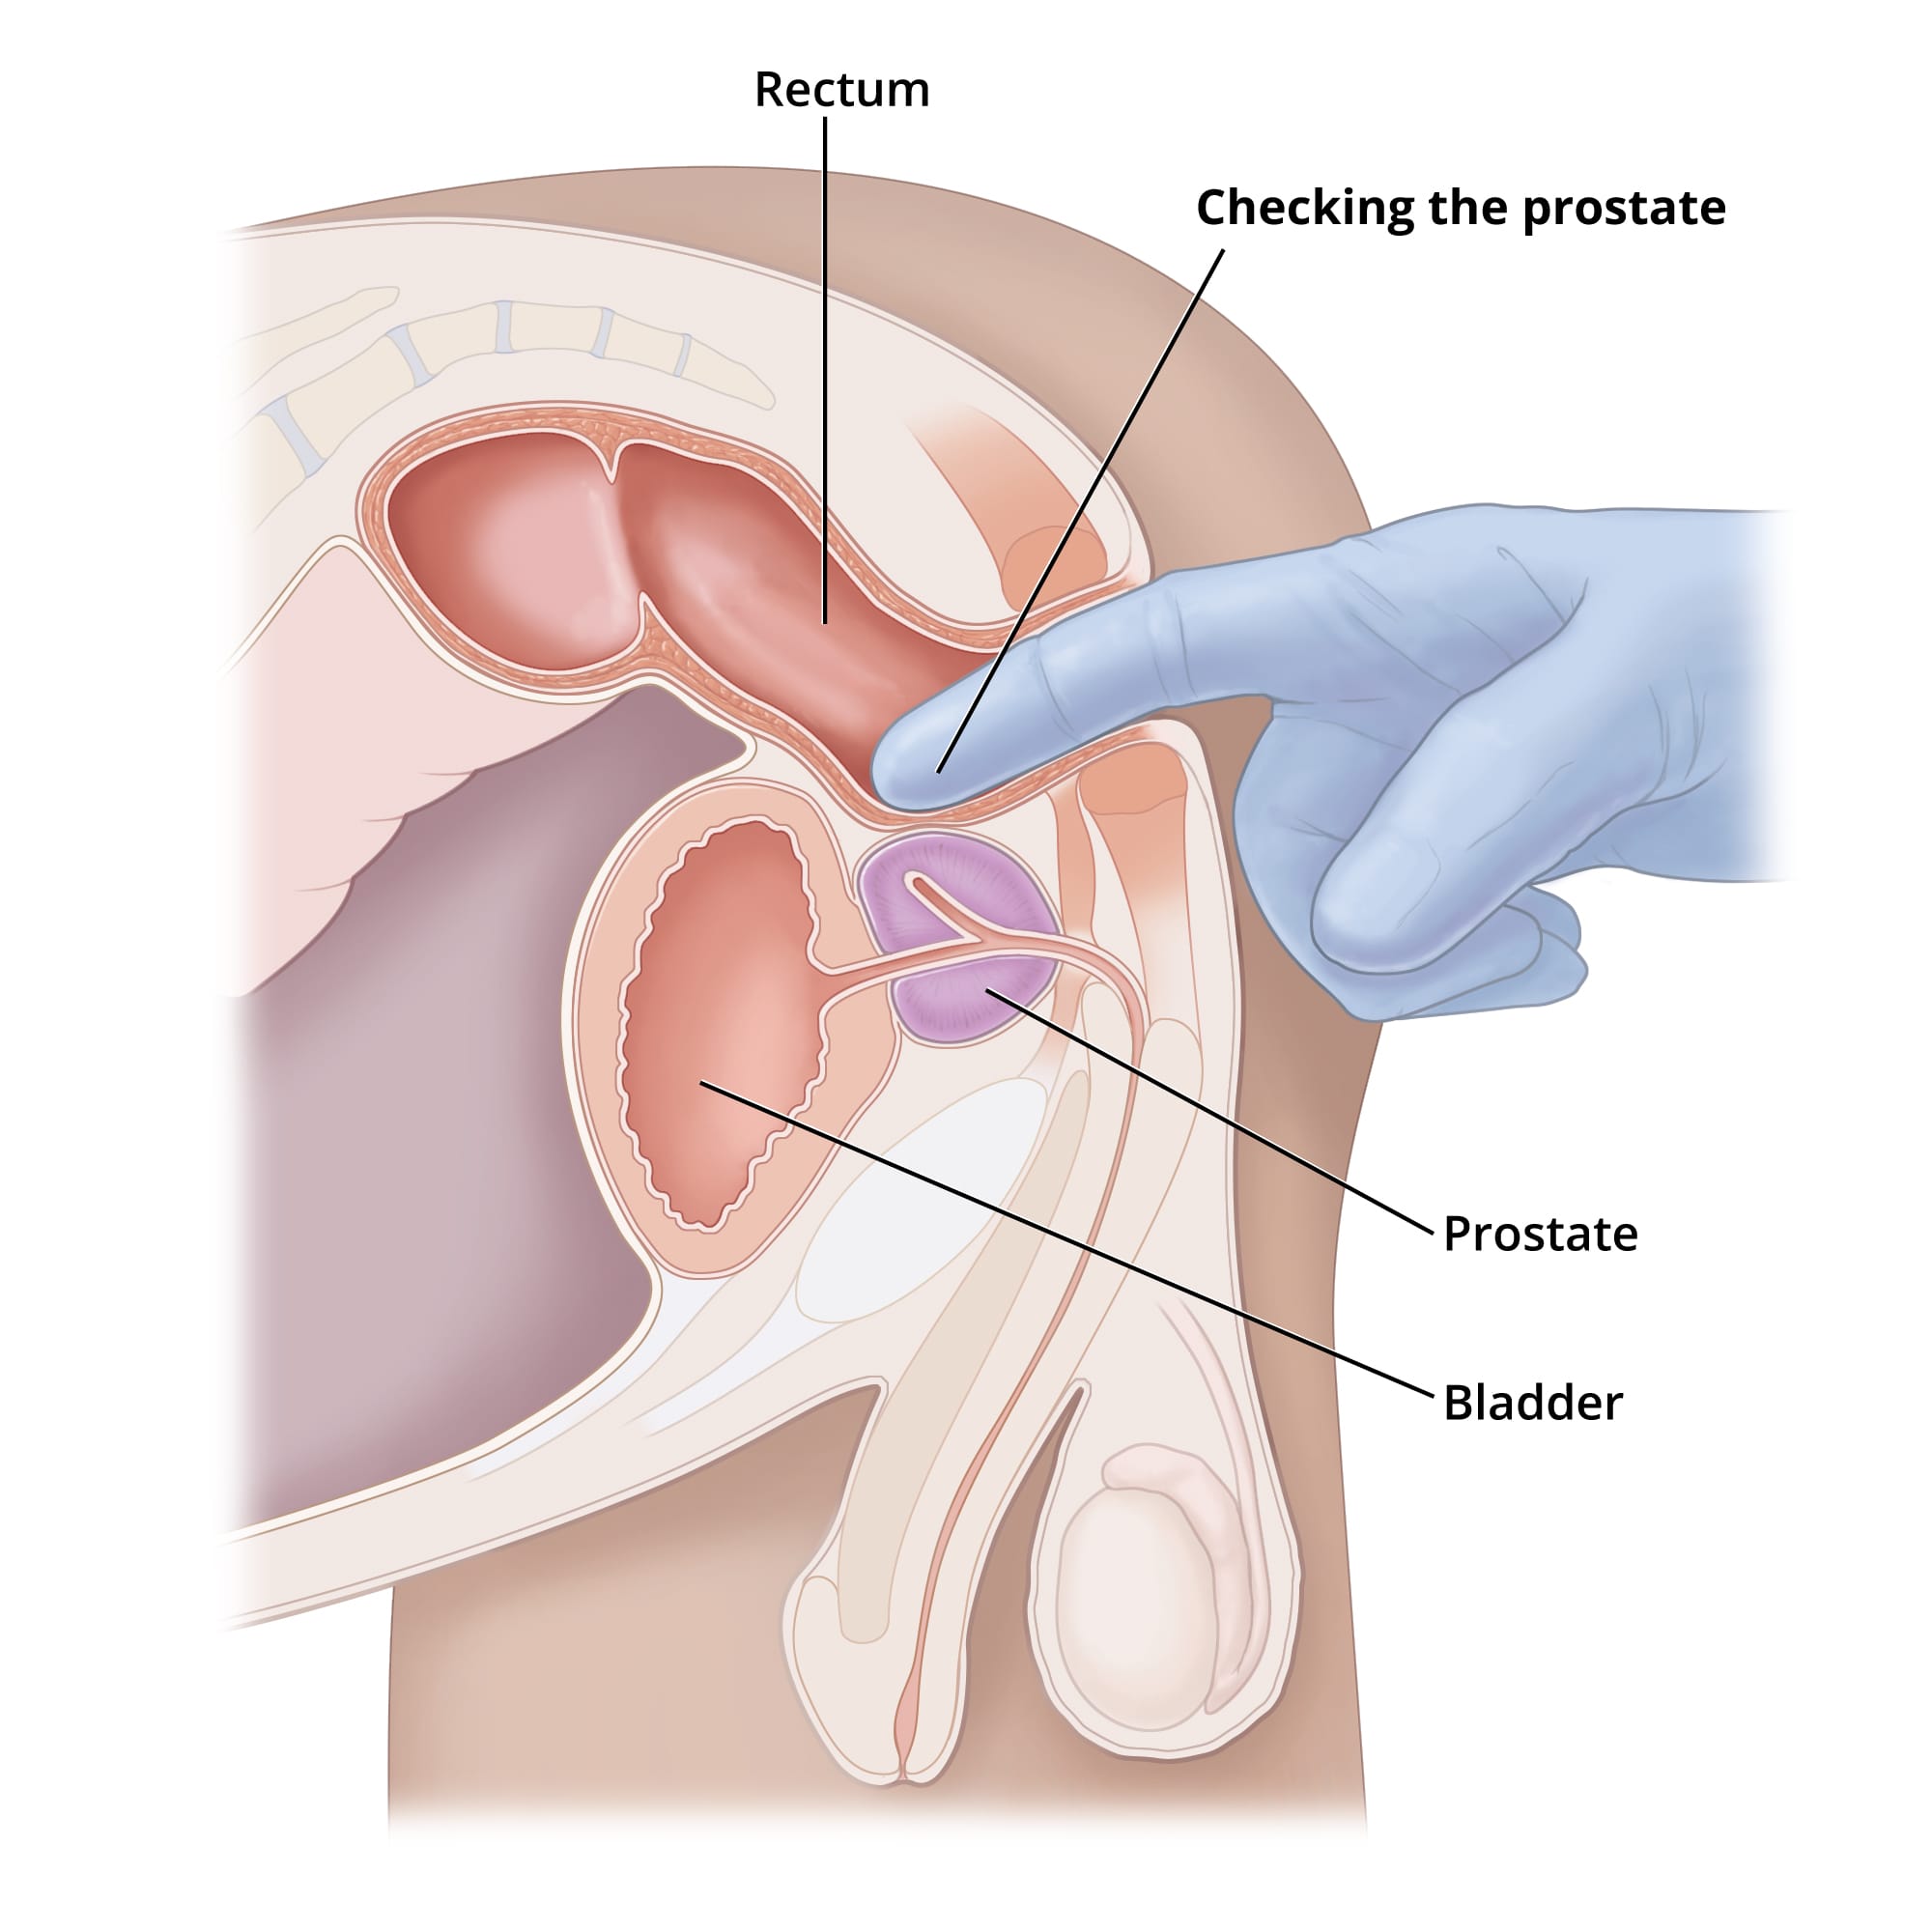
A prostate DRE uses a gloved, lubricated finger through the rectal wall to assess approximate prostate size, symmetry, texture and abnormal findings.
How is a digital rectal examination of the prostate performed?
A prostate DRE is performed by gently inserting a gloved, lubricated finger into the rectum and palpating the accessible prostate surface. The patient may stand and lean forward or lie on one side with the knees drawn toward the chest. The prostate lies just in front of the rectum, so its posterior surface can be palpated through the rectal wall.
The examination is usually brief. Pressure or short-lived discomfort can occur, particularly when the pelvic floor is tense or the prostate is tender. Severe pain is not expected and should be reported immediately. Sedation or pain medicine is not normally required.
Which units, thresholds or scoring rules are used for a prostate DRE?
A prostate DRE has no universal BPH numerical score; clinicians document approximate size, symmetry, consistency, tenderness and suspicious palpable abnormalities. Clinicians may describe the prostate as normal-sized or enlarged, estimate its dimensions, or provide a rough weight or volume category. These descriptions depend on the examiner and do not equal a measurement obtained by ultrasound or MRI.
The European Association of Urology notes that correlation between DRE estimates and measured prostate volume is poor. DRE commonly underestimates volume, and the underestimation becomes greater as the prostate enlarges, particularly above approximately 30 mL. Therefore, an apparently modest enlargement on examination should not be treated as an exact volume.
02. What Does a Prostate DRE Assess?
A prostate DRE assesses the accessible gland surface for enlargement, asymmetry, firmness, nodules and tenderness; it does not examine all prostate tissue.
What do different prostate findings mean?
Prostate DRE findings suggest different possibilities: smooth enlargement supports benign enlargement, while nodules, marked firmness or tenderness require interpretation and further assessment.
| Finding | Possible clinical meaning | What the finding does not establish |
|---|---|---|
| Smooth, symmetric enlargement | May support benign prostate enlargement when consistent with the rest of the evaluation. | Does not prove histologic BPH or show that enlargement is causing obstruction or symptoms. |
| Hard nodule, induration, marked asymmetry or irregularity | Can raise concern for malignancy and may lead to PSA testing, imaging or urologic assessment. | Does not diagnose prostate cancer; benign changes can sometimes feel abnormal. |
| Marked tenderness | May occur with prostatitis or another inflammatory process, especially when symptoms fit. | Does not identify the cause or confirm bacterial infection by itself. |
| No palpable abnormality | No abnormality was felt on the accessible surface. | Does not exclude enlargement, obstruction, inflammation or prostate cancer elsewhere in the gland. |
The examiner may also assess anal tone, rectal abnormalities or stool findings when clinically relevant. Those observations are separate from the prostate assessment.
Which factors can change or distort a DRE assessment?
Prostate DRE estimates vary with examiner experience, patient position and anatomy; ultrasound provides a more objective volume when size affects treatment. The estimate can be influenced by the clinician’s experience, the patient’s body position and anatomy, rectal stool, pelvic-floor tightening, discomfort, obesity and the size or shape of the gland. Only the portion reachable through the rectal wall can be felt. Anterior areas and some median-lobe enlargement may not be adequately assessed.
Temporary tenderness can also alter the examination. Acute inflammation may make palpation painful, while previous prostate surgery or treatment can change the gland’s contour and consistency. These factors should be documented rather than forcing the finding into a simple “normal” or “abnormal” label.
03. Prostate Exam: Reference Findings, Modifiers and Limitations
Prostate DRE findings require interpretation with symptoms, cancer risk, PSA when indicated and objective tests; normal palpation does not exclude prostate disease.
How should DRE be interpreted alongside other prostate findings?
Prostate DRE complements urinary symptoms, PSA, imaging and functional tests because palpation assesses texture and approximate anatomy rather than urine flow or residual volume. In a man with LUTS, DRE contributes an estimate of gland size and identifies findings that might redirect the evaluation. The International Prostate Symptom Score records symptom severity, while DRE assesses palpable anatomy. Neither measures urine flow or the amount of urine left in the bladder.
PSA may contribute information about prostate-cancer risk and, in the appropriate setting, can act as a rough marker of prostate volume or progression risk. Ultrasound or MRI provides a more reliable anatomical volume. Uroflowmetry assesses the pattern and rate of urine flow. A post-void residual test measures urine remaining after urination. Each test answers a different clinical question.
Urgent assessment is appropriate for inability to urinate, fever with pelvic or urinary symptoms, severe pain, visible blood in the urine, or rapidly worsening illness. A routine DRE result should never delay evaluation of these warning signs.
What can a DRE not diagnose or prove by itself?
A prostate DRE cannot confirm microscopic BPH, establish functional outlet obstruction or exclude prostate cancer by itself.
- Histologic BPH: BPH describes noncancerous microscopic growth of glandular and stromal tissue. A physical examination cannot confirm this tissue diagnosis.
- Benign prostate enlargement: DRE can suggest enlargement but cannot provide a precise volume, and some enlargement may be outside the easily palpable region.
- Benign prostatic obstruction: a large-feeling prostate does not prove resistance to urinary flow. Conversely, clinically important obstruction can occur without a dramatically enlarged gland.
- Cause of LUTS: urgency, frequency, nocturia, weak stream and incomplete emptying can arise from the bladder, urethra, neurologic disease, medicines, infection and other conditions.
- Prostate cancer: a suspicious finding increases concern but is not diagnostic. A normal DRE does not exclude cancer, especially disease that is small, anterior or otherwise not palpable.
These distinctions prevent a common error: using the words BPH, enlarged prostate, obstruction and LUTS as if they describe the same condition. They are related in some men, but they are not interchangeable.
04. How Does the Prostate Exam Affect the Next Clinical Decision?
Prostate DRE abnormalities guide further evaluation: suspected enlargement supports objective sizing, while suspicious texture or nodules prompt risk-based prostate assessment.
When should DRE be repeated, confirmed or combined with another test?
Prostate DRE is repeated when symptoms, risk factors or previous abnormalities need reassessment; PSA and imaging supplement palpation when clinically indicated. There is no single repeat interval that applies to every man with LUTS.
Further testing depends on the clinical question. A suspicious nodule or induration may prompt a prostate-cancer risk assessment that can include PSA, MRI and urology referral. Tenderness with fever or urinary symptoms may require urinalysis, urine culture and assessment for infection. When treatment selection depends on prostate size, imaging is more reliable than a DRE estimate.
How can DRE change the next step in BPH evaluation?
An enlarged prostate on DRE supports measuring prostate volume before size-dependent BPH treatment; suspicious findings require a separate diagnostic assessment. A relatively small-feeling gland with significant symptoms may prompt closer attention to bladder dysfunction, urethral narrowing or other causes. A suspicious or painful finding redirects evaluation away from assuming uncomplicated BPH.
The next step is therefore not determined by “large” or “normal” alone. Clinicians combine the DRE with symptom burden, quality-of-life impact, urinalysis, medication history, neurologic findings, PSA when appropriate, urine flow and residual urine. This approach separates a palpable prostate finding from the question of whether the bladder outlet is actually obstructed.
Summary
- A DRE is a brief examination of the prostate through the rectal wall.
- It assesses approximate size, symmetry, surface, consistency, tenderness and palpable abnormalities.
- There is no universal DRE score or reliable numerical volume threshold.
- A smooth enlarged gland may fit benign enlargement; a hard, nodular, irregular or markedly asymmetric gland requires further assessment.
- DRE cannot diagnose histologic BPH, prove urinary obstruction, identify the cause of LUTS or exclude prostate cancer.
- Abnormal or treatment-relevant findings are confirmed with tests selected for the clinical question.
Watch: How BPH is diagnosed
Prostate DRE provides palpable anatomical findings within BPH evaluation. FactBasedUrology explains how symptoms, examination and selected tests contribute to the broader diagnostic process in this video.
Evidence Sources
- European Association of Urology. Management of Non-neurogenic Male LUTS: Diagnostic Evaluation.
- National Institute of Diabetes and Digestive and Kidney Diseases. Prostate Tests.
- NIDDK. Enlarged Prostate (Benign Prostatic Hyperplasia).
- American Urological Association. Key Features of the Digital Rectal Exam.
- European Association of Urology. Prostate Cancer: Diagnostic Evaluation.