
Reproductive physiology · Semen biochemistry · Lower urinary tract
What Does the Prostate Do? Function in Semen, Ejaculation and Fertility
The prostate is best known because it enlarges, becomes inflamed or develops cancer. Its normal job is reproductive: secretory cells manufacture a distinctive fluid, ducts release it into the urethra, and smooth muscle helps propel the mixture during ejaculation. Its position around the urethra also gives it major urinary consequences, but filtering urine is not one of its functions.
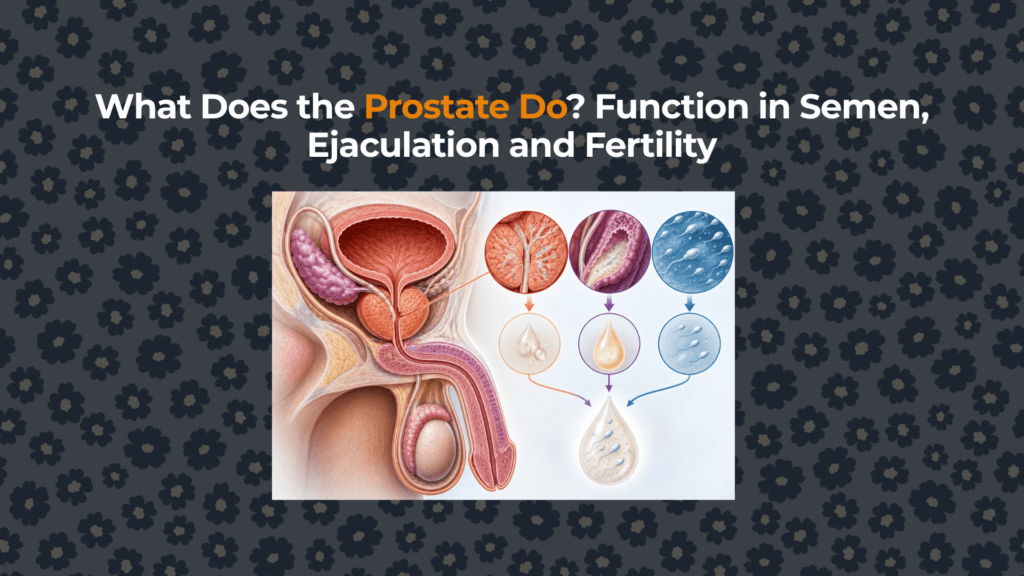
The prostate has three coordinated functions
A functional explanation begins with structure. Glandular acini manufacture fluid; branching ducts convey it; fibromuscular stroma contracts. These systems occupy the same organ but perform different tasks. The zonal distribution described in the prostate zone anatomy guide also matters: secretory peripheral-zone epithelium is particularly enriched in zinc and citrate metabolism, while transition-zone enlargement is more closely linked to obstruction.
Secretory epithelium makes PSA, citrate, zinc-rich fluid and other molecules.
Prostatic ducts empty into the urethra during emission.
Smooth muscle contracts with the reproductive tract during ejaculation.
What is in prostatic fluid?
Prostatic fluid is a complex secretion rather than a single nutrient solution. Its composition changes after mixing with fluids from the seminal vesicles, testes, epididymides and bulbourethral glands. Values also vary by collection method, abstinence interval, age, inflammation and laboratory technique.
| Component | Physiological role or association | Important qualification |
|---|---|---|
| Prostate-specific antigen (PSA/KLK3) | Serine protease that cleaves semenogelin proteins and promotes post-ejaculatory liquefaction | PSA in blood is a prostate marker, not a function score or cancer-specific molecule |
| Citrate | Major prostate secretion; complexes with zinc and participates in semen buffering and ion regulation | Normal prostate cells unusually accumulate rather than fully oxidize citrate |
| Zinc | Linked to citrate metabolism; binds seminal proteins and regulates several enzymes, including PSA activity | High prostate zinc does not mean oral zinc supplements improve prostate disease |
| Spermine and spermidine | Polyamines contributing to the chemical environment and characteristic odor of semen | Specific reproductive effects remain incompletely defined |
| Proteases and phosphatases | Participate in semen processing and provide measurable tissue/serum markers | Prostatic acid phosphatase is no longer the principal screening marker |
| Ions and water | Set fluid volume, osmolality and biochemical conditions for sperm | Final semen pH reflects all accessory-gland contributions, especially seminal-vesicle fluid |
How does PSA liquefy semen?
The seminal vesicles release semenogelin proteins that help freshly ejaculated semen form a temporary coagulum. The prostate releases PSA, an enzyme capable of cleaving those proteins. Proteolysis breaks down the gel network and semen becomes more fluid, generally freeing sperm from the coagulum.
This is PSA’s normal reproductive role. A small amount crosses tissue barriers into blood, where laboratories measure total and free PSA for prostate assessment. Blood PSA can rise with cancer, BPH, inflammation and prostate manipulation; it is organ-associated rather than cancer-specific.
Why does the prostate accumulate citrate and zinc?
Most cells oxidize citrate in mitochondria to extract energy. Differentiated prostate secretory cells are unusual: they accumulate high zinc concentrations, which inhibit mitochondrial aconitase and limit citrate oxidation. The cells therefore produce and release large quantities of citrate at an energetic cost.
A review reported citrate concentrations of roughly 40–150 μmol/g in prostatic fluid compared with about 0.09–0.11 μmol/g in blood plasma when expressed in the source’s wet-weight-equivalent table—an approximately three-order-of-magnitude contrast. Exact values and units differ across methods, so the biological conclusion is stronger than any one numerical ratio: normal secretory prostate tissue is exceptionally citrate- and zinc-rich.
What happens during ejaculation?
Ejaculation has two coordinated phases. During emission, sympathetic signaling moves sperm through the vas deferens and triggers accessory-gland secretion into the posterior urethra. Prostate stromal and capsular smooth muscle contracts, squeezing fluid from acini through ducts. During expulsion, rhythmic pelvic-floor and urethral-muscle contractions propel semen outward.
The bladder neck normally closes to limit backward flow into the bladder. Damage, surgery or medicines that reduce bladder-neck contraction can cause retrograde ejaculation. That is distinct from erectile dysfunction: erection depends mainly on penile vascular and neural mechanisms, not prostate secretion.
Does the prostate control urination?
No, but its anatomy can alter urine flow. The proximal urethra passes through the gland, as shown in the prostatic urethra and bladder-outlet guide. Transition-zone growth can increase outlet resistance; smooth-muscle tone can add a dynamic component. The bladder muscle still generates the pressure that moves urine.
The prostate does not
- make, store or filter urine
- serve as the primary urinary sphincter
- cause every urinary symptom
- determine obstruction by size alone
The prostate can
- change urethral geometry
- increase outlet resistance when enlarged
- contribute smooth-muscle tone
- affect urinary and ejaculatory pathways simultaneously
Does the prostate make sperm or testosterone?
No. Testes produce sperm and most circulating testosterone. The prostate responds to androgens: the enzyme 5α-reductase converts testosterone to dihydrotestosterone within prostate tissue, and androgen-receptor signaling supports gland growth and secretion. This is why 5α-reductase inhibitors can shrink BPH tissue and may reduce semen volume, but it does not make the prostate an endocrine source of testosterone.
Is the prostate essential for fertility?
Prostatic fluid supports normal semen processing and sperm function, but fertility is a system outcome. It also depends on sperm production, duct patency, seminal-vesicle secretion, ejaculation, sexual function and female-partner factors. A person can produce sperm after prostate removal, yet natural conception through intercourse is no longer possible because the reproductive ducts have been divided and semen is not ejaculated.
Before radical prostate surgery, pelvic radiotherapy or certain systemic treatments, people who may want biological children should discuss sperm banking. Treatment consequences differ from the effects of untreated prostate cancer itself.
How do BPH, prostatitis and cancer alter function?
| Condition | Main functional change | What cannot be inferred |
|---|---|---|
| BPH | Transition-zone nodules may narrow or distort the urethral outlet; glandular and stromal proportions change | Large volume does not automatically equal severe obstruction |
| Prostatitis | Inflammation may cause pain, urinary symptoms, PSA elevation and altered secretions | Symptoms alone do not identify bacterial infection |
| Prostate cancer | Malignant cells commonly lose differentiated zinc/citrate accumulation; local growth may affect ducts and adjacent tissue | Low zinc or citrate in an individual semen sample cannot diagnose cancer |
| Prostatectomy | Removes prostate secretion and normally eliminates semen ejaculation | It does not directly remove testosterone production |
| Radiation/medication | May alter secretion, ejaculate volume, erections, fertility or urinary function | Effects vary by treatment, dose, anatomy and baseline health |
For symptom-specific interpretation, the prostatitis hub separates acute infection, chronic bacterial disease and chronic pelvic pain patterns.
Summary
The prostate is a secretory and muscular reproductive gland. It produces about one-quarter of semen volume, supplies PSA that helps liquefy the seminal coagulum, and specializes in citrate–zinc metabolism. During emission, its ducts and smooth muscle add and propel fluid. Its urinary importance comes from surrounding the urethra, not from producing urine. These functions explain why prostate disease and treatment can influence ejaculation, fertility and urinary flow through different mechanisms.
General medical education only; this article cannot diagnose urinary, fertility or prostate conditions.


