
How Can BPH Cause Urinary Urgency? Bladder Outlet Obstruction and Storage Symptoms
Urgency is not simply needing to urinate. The International Continence Society defines it as a sudden, compelling desire to void that is difficult to defer. BPH can contribute by changing outlet resistance, bladder muscle behavior and sensory signaling.
Normal filling sensation rises gradually; urgency behaves differently
During normal storage, bladder-wall stretch generates progressively stronger afferent signals while the detrusor remains relaxed and the outlet stays closed. Urgency is a difficult-to-defer signal that can occur at a lower-than-expected volume. It may reflect bladder oversensitivity without a measurable contraction, or coexist with detrusor overactivity.
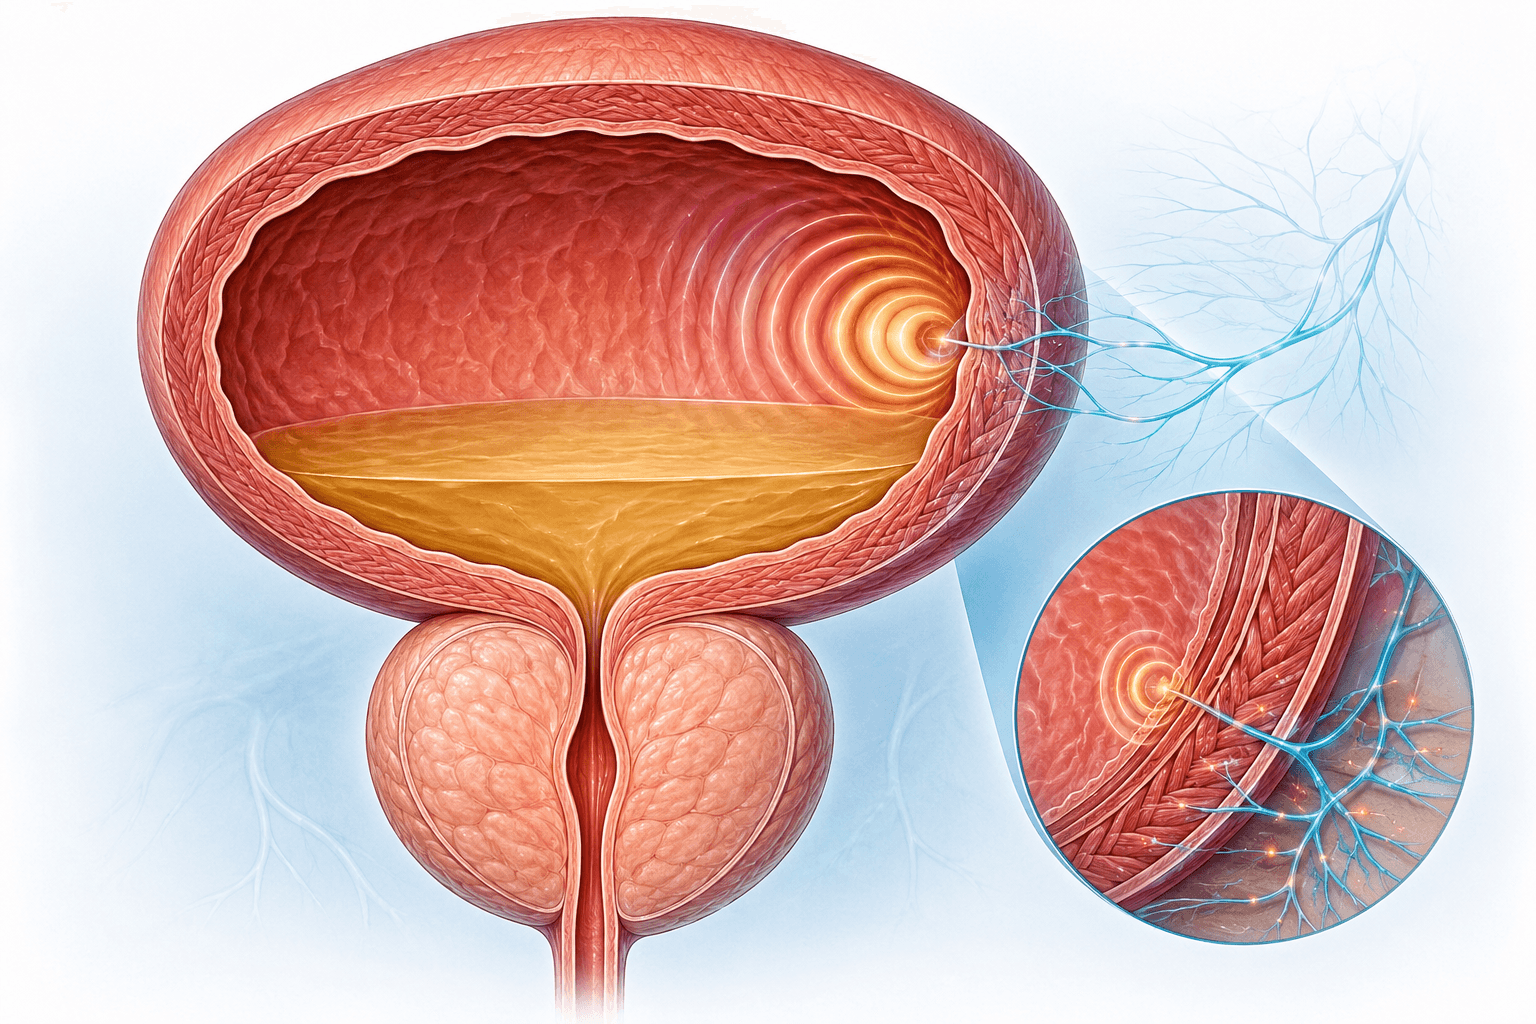
How can an enlarged prostate influence bladder signaling?
BPH develops around the urethra, but urgency is experienced through the bladder–nervous-system pathway. The relationship is therefore indirect and variable. The BPH hub distinguishes histologic growth from enlargement and functional obstruction.
| Proposed pathway | Biological change | Clinical expression | What it does not prove |
|---|---|---|---|
| Pressure load | Detrusor works against outlet resistance | Wall remodeling; altered storage | That every enlarged gland obstructs |
| Afferent amplification | Filling signals may be perceived earlier | Difficult-to-defer urge at lower volume | A detrusor contraction |
| Detrusor overactivity | Involuntary pressure rise during filling | Urgency with or without leakage | That BPH caused the contraction |
| Residual urine | Less usable capacity remains after voiding | Earlier refill threshold | Obstruction rather than weak contraction |
Urgency, frequency and detrusor overactivity are not interchangeable
| Term | Type | Meaning | How established |
|---|---|---|---|
| Urgency | Symptom | Sudden compelling desire to void that is difficult to defer | Patient report |
| Frequency | Symptom | Voiding more often than considered normal | Report + diary |
| Urgency urinary incontinence | Symptom | Leakage accompanied or immediately preceded by urgency | Patient report/diary |
| Overactive bladder | Symptom syndrome | Urgency, usually with frequency/nocturia, with or without urgency incontinence, absent obvious pathology | Clinical evaluation |
| Detrusor overactivity | Urodynamic observation | Involuntary detrusor contraction during filling | Cystometry |
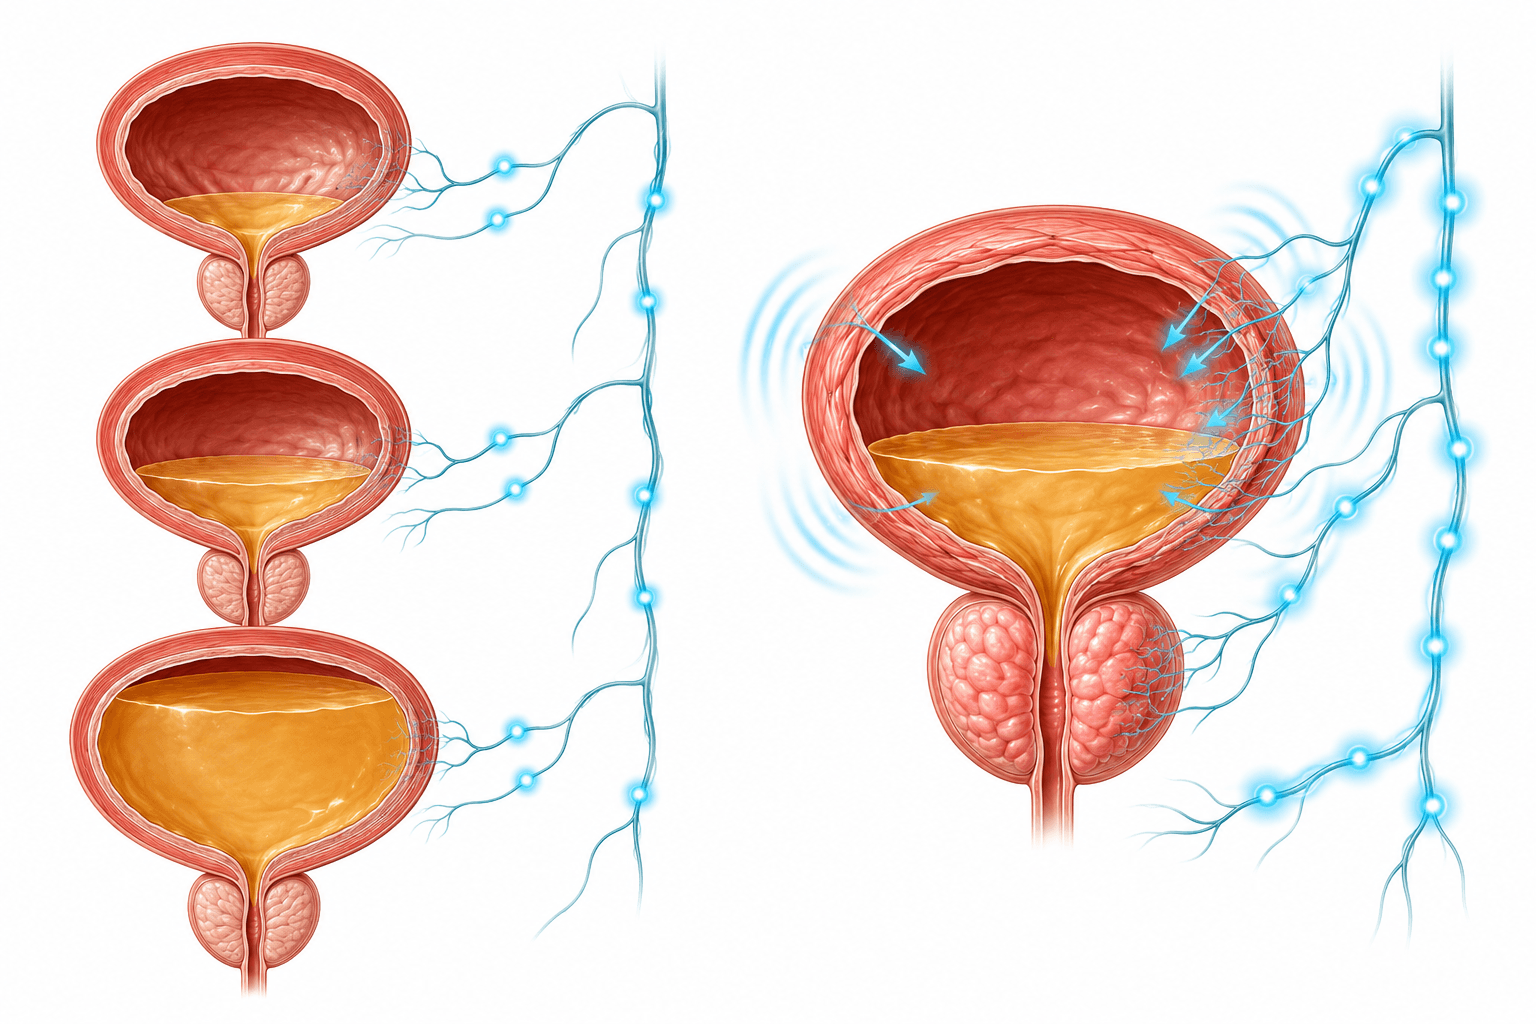
Which findings support a prostate contribution?
Urgency becomes more compatible with a prostate-linked mixed pattern when it coexists with reduced flow, elevated post-void residual, enlarged/protruding outlet anatomy or pressure–flow evidence of obstruction. Yet storage severity correlates imperfectly with obstruction. The preceding frequency article shows how a diary separates count from volume; the weak-stream page explains objective flow limits.
What evaluation goes beyond the prostate?
| Evidence layer | Question answered | Boundary |
|---|---|---|
| History + medication review | Onset, triggers, pain, intake, neurologic/systemic context | Symptoms overlap across causes |
| Urinalysis/culture when indicated | Infection, blood or metabolic clues | A normal result does not prove BPH |
| Three-day bladder diary | Timing, volume, urgency and leakage pattern | Cannot measure outlet pressure |
| PVR + uroflow | Emptying and flow performance | Do not separate obstruction from weak contraction alone |
| Urodynamics | Detrusor overactivity, pressure–flow mechanism | Reserved for selected uncertainty |
Will treating BPH remove urgency?
It may improve urgency when outlet resistance and secondary bladder effects are important. Alpha blockers target dynamic tone; selected enlarged glands may benefit from 5-alpha-reductase inhibition; procedures widen the outlet. Persistent urgency can require a bladder-directed strategy. EAU guidance supports antimuscarinic or beta-3 agonist therapy for appropriate men with predominant storage LUTS, with attention to residual urine and individual risk. The next bridge covers BPH and urinary hesitancy.
When is urgency urgent?
Evidence synthesis
BPH can contribute to urinary urgency through outlet-related pressure load, bladder remodeling, altered afferent signaling, detrusor overactivity or reduced usable capacity from residual urine. Urgency remains a symptom—not proof of BPH, obstruction or an involuntary detrusor contraction. A diary, urinalysis, PVR, uroflow and selected urodynamics identify the dominant prostate, bladder, urethral or systemic mechanism.
Educational information only. Individual diagnosis and treatment require qualified clinical assessment.


