BPH treatment uses observation, medicines or procedures according to symptom burden, prostate anatomy, bladder function, complications and patient goals; gland size or symptom score alone does not determine the treatment.

01. Benign Prostatic Hyperplasia: Treatment Options and Decision Factors
BPH treatment ranges from monitoring and self-care to medicines or procedures, selected according to symptoms, prostate anatomy, bladder emptying, complications and patient priorities.
Which management or treatment categories are used for benign prostatic hyperplasia?
BPH management uses watchful waiting, alpha blockers, 5-alpha-reductase inhibitors, tadalafil, bladder-directed medicines or procedures to address different symptoms and risks.
| Category | Best aligned clinical problem | Main limitation |
|---|---|---|
| Watchful waiting and self-care | Mild or moderately bothersome uncomplicated LUTS with acceptable risk | Requires follow-up; symptoms or residual urine may progress. |
| Alpha-1 blockers | Faster improvement of moderate-to-severe LUTS | Do not shrink the prostate or prevent long-term retention/surgery. |
| 5-alpha-reductase inhibitors | Enlarged prostate with increased progression risk | Slow onset; sexual adverse effects and PSA interpretation changes. |
| Storage-symptom medicines | Urgency, frequency or urgency incontinence after assessing emptying | Require PVR and adverse-effect review in appropriately selected men. |
| PDE5 inhibitor | Male LUTS, particularly when erectile dysfunction coexists | Contraindicated with nitrates; effect on measured obstruction is limited. |
| Minimally invasive or surgical treatment | Complications, persistent bother, objective obstruction or preference for durable relief | Suitability and sexual, bleeding, anaesthetic and retreatment risks vary. |
When is observation or conservative management appropriate?
Observation is appropriate when symptoms are mild or acceptable, evaluation shows no urgent complication and the patient understands follow-up. The EAU strongly recommends watchful waiting for men with mild-to-moderate LUTS who are minimally bothered. Useful measures include timing fluid intake, moderating caffeine and alcohol, treating constipation, reviewing medicines, relaxed or double voiding and monitoring change.
Conservative care is active management, not neglect. Increasing bother, recurrent retention, infection, stones, haematuria, renal impairment or a rising residual should trigger reassessment.
02. How Is Benign Prostatic Hyperplasia Managed or Treated?
BPH is managed by matching observation, medicines or procedures to the demonstrated urinary problem and reassessing whether treatment improves the intended outcome.
Which medicines and procedures are used for benign prostatic hyperplasia?
BPH medicines include alpha blockers, finasteride or dutasteride, tadalafil and selected bladder therapies; procedures relieve outlet resistance through tissue removal, retraction, shrinkage or reduced arterial supply. EAU trials show typical IPSS reductions of about 30–40% and Qmax increases of 20–25%, but they do not reduce prostate size or prevent long-term retention.
Finasteride and dutasteride are 5-alpha-reductase inhibitors for men with enlargement and higher progression risk. After two to four years, the EAU reports approximately 15–30% IPSS improvement, 18–28% prostate-volume reduction and a 1.5–2.0 mL/s Qmax increase. They also reduce long-term acute-retention and surgery risk. Antimuscarinics or beta-3 agonists target storage symptoms in selected men; tadalafil can improve male LUTS with or without erectile dysfunction.
Procedures include prostate-lifting or water-vapour approaches for selected anatomy, endoscopic resection or incision, laser vaporisation or enucleation, waterjet ablation, prostate-artery embolisation in selected settings, and simple prostatectomy for some very large glands. Each technique has separate selection criteria and should not be treated as interchangeable.
How do symptoms, anatomy and disease risk affect treatment choice?
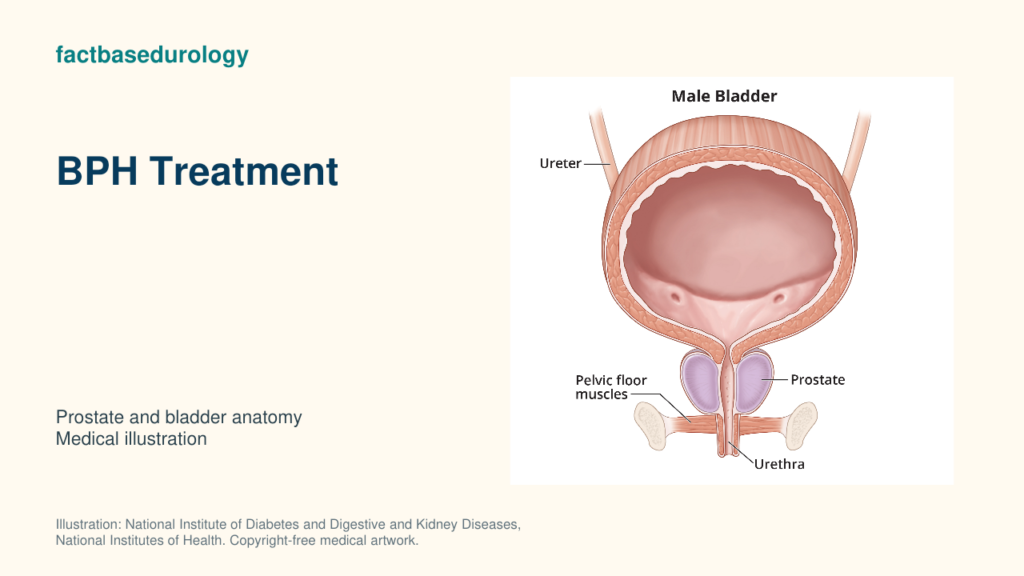
BPH treatment selection changes with voiding versus storage symptoms, gland volume, median-lobe anatomy, bladder contraction, retention and other urinary complications. Prostate volume and median-lobe anatomy affect medication benefit and procedural eligibility. Recurrent retention, bladder stones, recurrent infection, treatment-resistant bleeding or upper-tract effects strengthen the case for intervention. Detrusor underactivity can reduce expected benefit even when resistance is relieved.
03. Benign Prostatic Hyperplasia: Treatment Selection, Outcomes and Trade-offs
BPH treatment comparisons assess symptom relief, emptying, progression risk, durability and sexual outcomes alongside drug adverse effects and procedural recovery.
What outcomes matter when comparing management options?
BPH treatment outcomes include symptom burden, quality of life, urinary flow, residual urine, retention risk, durability, retreatment and preservation of continence and sexual function. A large IPSS change is valuable only if it improves the symptoms and activities that matter to the patient.
Which adverse effects or trade-offs should be considered?
BPH treatment trade-offs include drug-related dizziness, sexual effects and PSA changes, or procedure-related bleeding, infection, recovery and retreatment risks.
| Option | Important trade-offs | Monitoring point |
|---|---|---|
| Alpha blocker | Dizziness, orthostatic hypotension, ejaculatory dysfunction; floppy-iris risk around cataract surgery | Blood pressure, falls, urinary response; inform eye surgeon. |
| 5-ARI | Reduced libido, erectile/ejaculatory effects, breast symptoms; slow benefit | PSA falls about 50% by 6–12 months and needs adjusted interpretation. |
| Antimuscarinic | Dry mouth, constipation, possible rising residual urine | Symptoms and PVR; EAU advises against use when PVR exceeds 150 mL. |
| Procedure | Bleeding, infection, stricture, incontinence, ejaculatory change, anaesthetic and retreatment risks vary | Match technique, anatomy, risk and desired durability. |
04. How Is the Best-Fit Management Strategy Chosen for Benign Prostatic Hyperplasia?
A suitable BPH management strategy targets the patient’s main symptoms and risks, fits prostate anatomy and balances expected benefit with adverse effects, durability and personal priorities.
When should treatment be changed, escalated or de-escalated?
BPH treatment needs review when an adequate trial fails, adverse effects outweigh benefit, adherence or goals change, or retention and other complications develop. Escalate promptly for recurrent or refractory retention, recurrent infection, bladder stones, treatment-resistant visible haematuria or renal/upper-tract consequences attributed to obstruction. De-escalation may be reasonable when symptoms remain controlled and the original indication no longer applies, but medication should be reviewed with the prescriber.
How should response be monitored over time?
BPH response is monitored with symptom burden, adverse effects and selected flow, residual-urine or PSA assessments linked to the treatment’s original goal. After a procedure, monitor symptom relief, emptying, infection, bleeding, continence, sexual outcomes and need for retreatment. New haematuria, pain, infection or neurologic symptoms requires a fresh diagnosis rather than assuming BPH progression.
Summary
- Observation, medicines and procedures address different BPH-related problems.
- Prostate size, symptom score and obstruction are related but not interchangeable.
- Alpha blockers act quickly; 5-ARIs act slowly and reduce progression risk in appropriately selected enlarged prostates.
- Best-fit treatment balances benefit, complications, anatomy, sexual priorities, adverse effects and durability.
Educational disclaimer: This article provides general medical education and cannot select treatment for an individual or replace assessment by a qualified clinician.
Watch: BPH treatment options
FactBasedUrology compares BPH treatment options in an educational video that expands the treatment context of this guide.