
What Is Intravesical Prostatic Protrusion (IPP)? Median Lobe Growth and Bladder Outlet Obstruction
IPP turns outlet geometry into a millimetre measurement. Its value comes from adding anatomical probability—not from replacing symptoms, flow or pressure–flow evidence.
01. IPP Is a Shape Measurement, Not a Disease Diagnosis
IPP describes the relationship between the prostate base and bladder lumen. It can reflect a protruding median lobe, central adenoma or combined lobe configuration. It does not identify cellular histology and is not synonymous with benign prostatic hyperplasia.
The preceding median-lobe enlargement article owns the ball-valve anatomy and procedure implications. This page owns how protrusion is measured and interpreted.
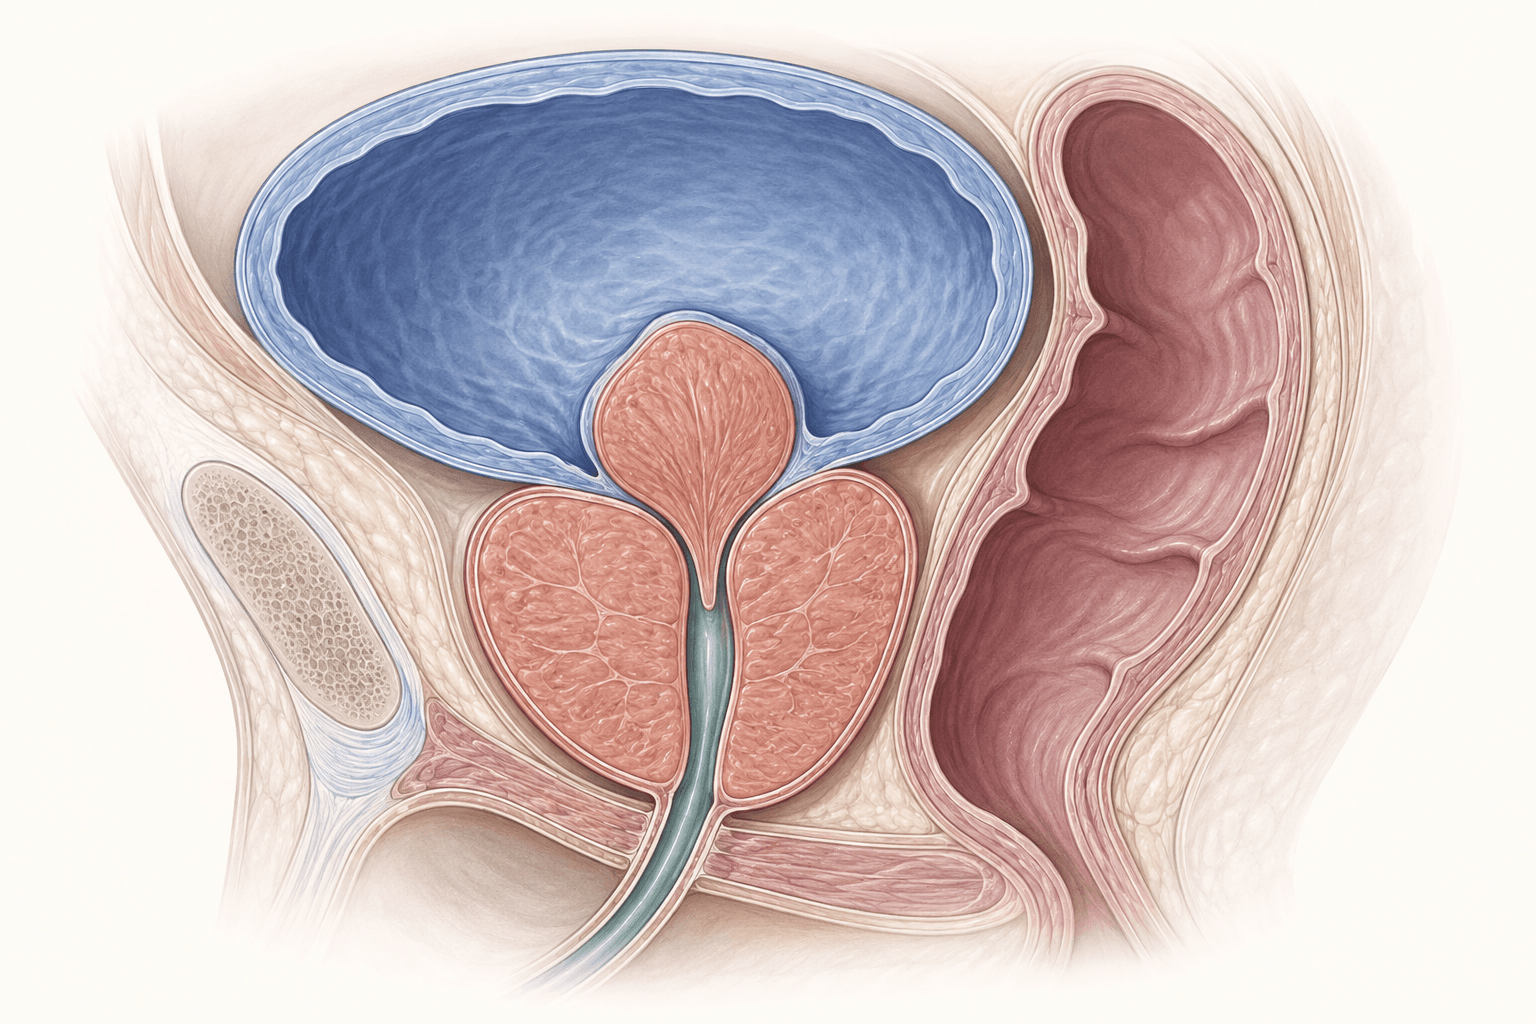
02. Ultrasound Measures IPP From the Bladder Base to the Protrusion Tip
On a sagittal image, the operator identifies the bladder base where the prostate circumference meets the bladder and draws a reference line across that base. IPP is measured perpendicularly from this line to the most intravesical tip. The result is recorded in millimetres.
03. Bladder Filling and Imaging Plane Can Change the Number
An underfilled bladder may obscure the base; excessive filling can flatten or alter protrusion. Published protocols have used different target volumes. One clinical review advises avoiding an empty or very full bladder above 400 mL and describes 100–200 mL as a practical range; a 2026 study found its most consistent measurements at 200–299 mL. These are study/protocol observations, not one universal cutoff.
A report should therefore record bladder volume when available, transabdominal versus transrectal route, image plane and the measured distance. Repeated measurements are most comparable when technique is similar.
04. Common IPP Grades Organize Millimetres Without Creating Biological Certainty
| Common grade | Measurement | Interpretive role | Do not infer |
|---|---|---|---|
| Grade 1 | ≤5 mm | Low protrusion in the common three-grade system | No BPH or no obstruction |
| Grade 2 | >5–10 mm | Intermediate projection | A universal treatment threshold |
| Grade 3 | >10 mm | High protrusion; raises BOO probability | Confirmed BOO or mandatory surgery |
Boundary handling differs across publications—for example, exactly 5 mm may be assigned differently. The raw millimetre result is more portable than grade alone.
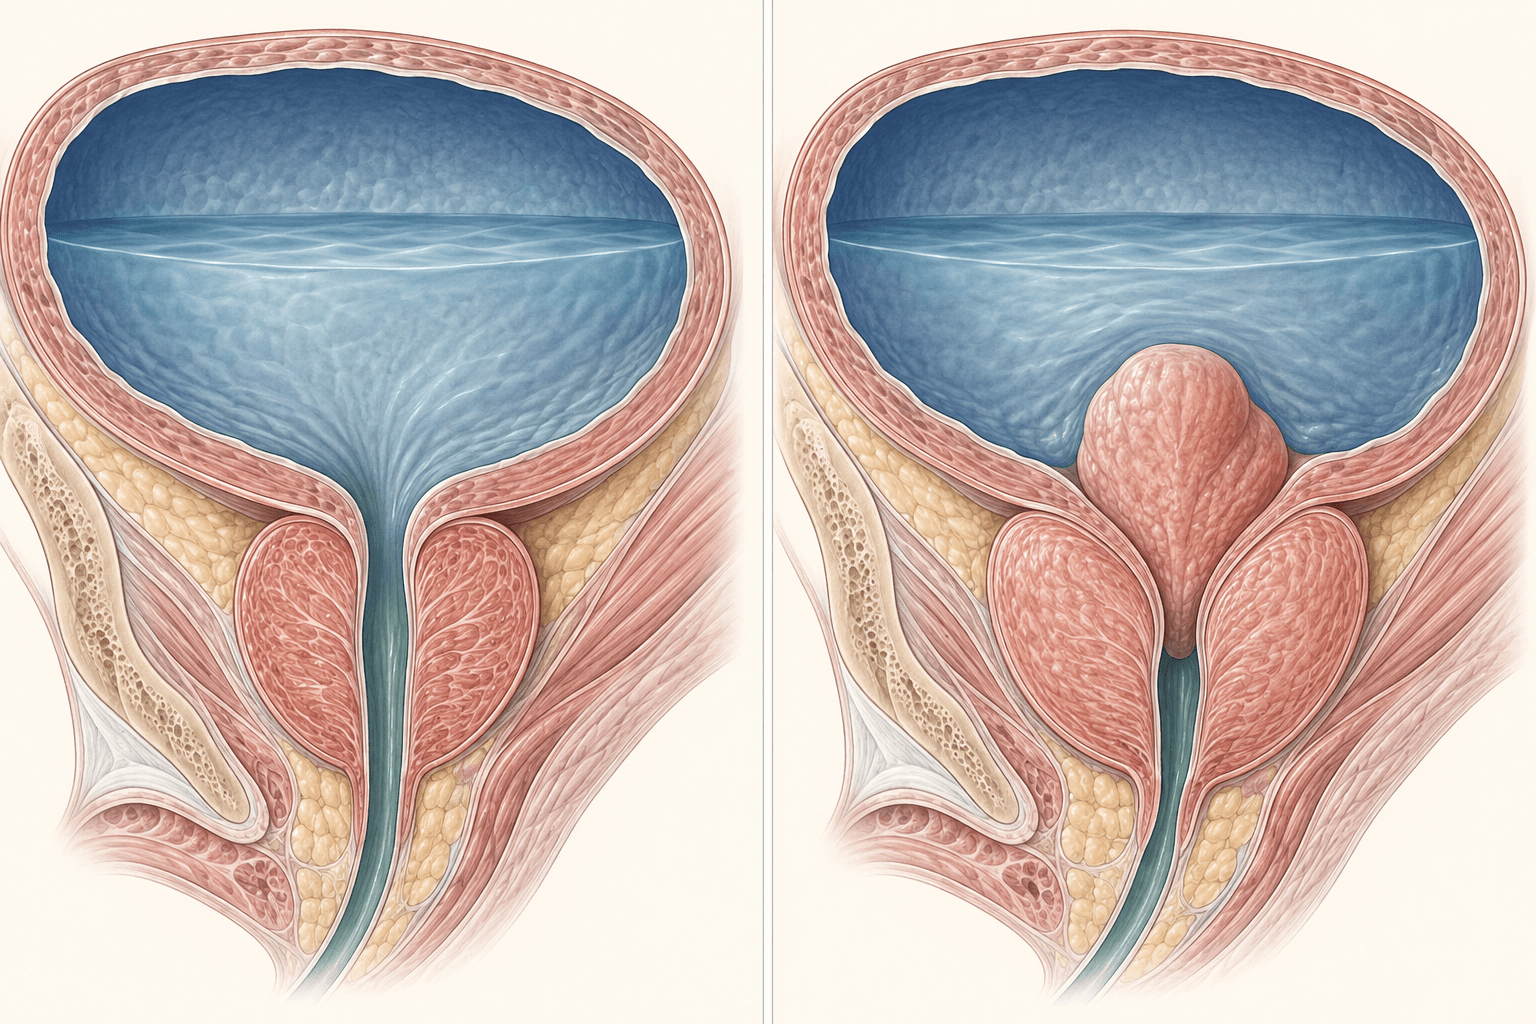
05. IPP Predicts BOO Better Than Chance but Misses and Misclassifies Cases
The EAU diagnostic-evaluation chapter reports sensitivity 0.71 and specificity 0.77 for an IPP cutoff above 10 mm against urodynamically determined obstruction. A 2026 diagnostic meta-analysis across thresholds around 10–12 mm found pooled sensitivity 71.0%, specificity 75.5% and summary ROC area 0.795—moderate diagnostic accuracy.
Between-study thresholds, ultrasound technique, case mix and obstruction definitions varied. The summary result supports IPP as an adjunct, not a universal replacement test.
06. Sensitivity and Specificity Explain What a 10 mm Threshold Can—and Cannot—Do
Using the 2026 pooled estimates in a purely educational group of 100 men—50 with and 50 without urodynamic BOO—IPP would identify about 36 of 50 obstructed men and miss about 14. It would classify about 38 of 50 unobstructed men correctly and label about 12 positive. Real predictive values change with BOO prevalence and patient selection.
07. IPP, Prostate Volume, IPSS, Qmax and PVR Remain Distinct Variables
| Variable | Unit/entity | Primary question | Relationship to IPP |
|---|---|---|---|
| IPP | Millimetres; outlet geometry | How far does tissue project into the bladder? | Central measure |
| Prostate volume | mL; total anatomy | How large is the gland? | May correlate, but size does not encode projection |
| IPSS | 0–35; symptom burden | How frequent/bothersome are seven LUTS? | Can be discordant with IPP |
| Qmax | mL/s; maximum flow | How fast is peak free flow? | Often decreases as IPP rises, but contractility matters |
| PVR | mL; emptying result | How much urine remains? | May increase, but cannot distinguish obstruction from underactivity |
| Pressure–flow | Pressure paired with flow | Is outlet resistance present? | Functional reference when confirmation is needed |
The prostate-volume article owns size measurement. The prostatic-urethra guide locates the channel affected by protrusion.
08. IPP May Modify Medication and Trial-Without-Catheter Expectations
Observational studies associate higher IPP with a lower chance of symptom improvement from alpha-blocker monotherapy and a lower probability of successful catheter removal after acute urinary retention. These findings can inform counseling and follow-up intensity, but they do not prove that every high-IPP patient will fail medication or require a procedure.
09. Pressure–Flow Testing Remains the Functional Reference When Certainty Matters
Symptoms, free flow, residual urine and IPP can all raise or lower suspicion. Pressure–flow urodynamics pairs detrusor pressure with urinary flow and most directly classifies outlet resistance. It is not required for every uncomplicated LUTS presentation; it is most valuable when the mechanism is uncertain and the answer could change invasive treatment.
The BPH-versus-BPO analysis explains this evidence ladder without treating BOO and BPO as synonyms.
10. A Useful Report Preserves Technique, Number, Grade and Clinical Context
Report the exact IPP in millimetres, the grade convention, route and plane, bladder volume or filling state, prostate volume and any visible median/lateral-lobe configuration. Interpret alongside symptoms, Qmax, PVR, retention history and the reason the test was ordered.
Continue to BPH-associated symptom patterns for the next mapped task. The urinary-health hub covers non-prostate causes of LUTS.
Evidence sources
- EAU 2026 Male LUTS Guideline: IPP diagnostic evaluation.
- Han et al., 2026: IPP diagnostic systematic review and meta-analysis.
- Tan et al.: transabdominal ultrasound IPP systematic review.
- Clinical considerations for IPP.
- Clinical value and measurement conditions for IPP.
- IPP and alpha-blocker treatment response.


