
Prostate anatomy · Zonal model · Updated August 26, 2026
What Are the Zones of the Prostate? Peripheral, Transition and Central Anatomy
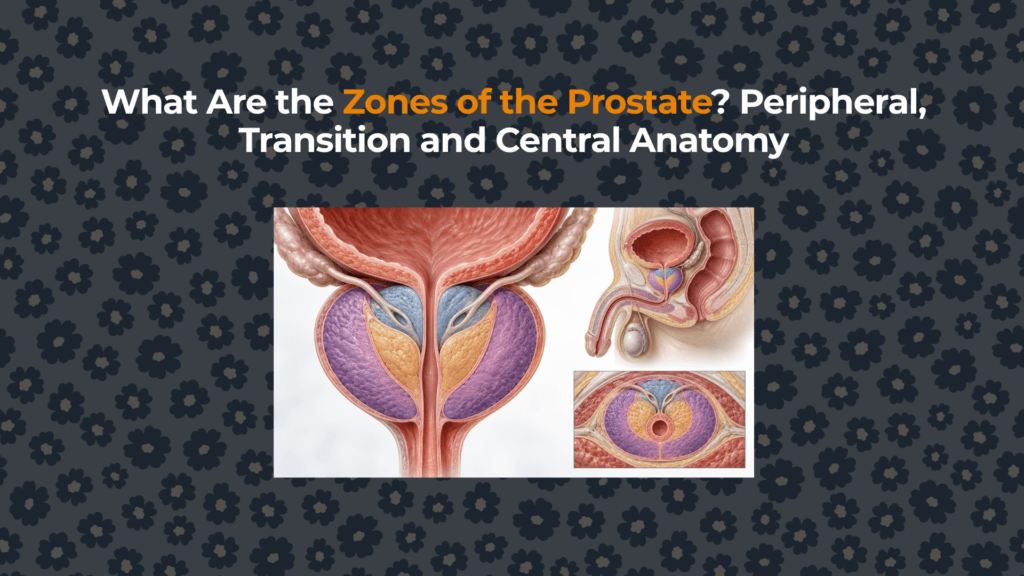
The prostate is organized into regions with different positions, tissue composition and disease patterns. Understanding those regions explains why benign enlargement commonly develops around the urethra while many prostate cancers arise farther back, near the rectum.
What is meant by a prostate “zone”?
A zone is a three-dimensional anatomical region defined by its relationship to the urethra and ejaculatory ducts, its microscopic gland pattern and its characteristic disease tendencies. Zones are not separate organs and do not have hard walls. They interlock within the same prostate and may become distorted when one region enlarges.
The zonal model was developed by pathologist John McNeal and is the principal framework used in pathology and prostate MRI. Before learning zones, it helps to understand where the prostate sits between the bladder, urethra and rectum.
What is the peripheral zone?
The peripheral zone forms most of the posterior and lateral gland and extends toward the apex. In young adults it accounts for roughly 70% of glandular tissue. Because its posterior surface lies nearest the rectum, part of it is accessible during digital rectal examination. On normal T2-weighted MRI it often has relatively high signal because of its fluid-rich ducts and acini.
The peripheral zone is clinically important because approximately 60–75% of prostate cancers are reported to originate there. This is a population-level distribution, not a prediction that a particular peripheral-zone finding is malignant. Inflammation, hemorrhage and benign changes can also alter peripheral-zone MRI signal. The dedicated peripheral-zone anatomy article develops this cancer-relevance boundary in detail.
What is the transition zone?
The transition zone consists of paired lobules surrounding the proximal prostatic urethra above the verumontanum. It contributes only about 5% of glandular tissue in many young adults, yet it can become the dominant part of an older enlarged prostate.
Benign prostatic hyperplasia originates mainly in transition-zone and periurethral tissue. As nodules expand, they can compress the urethral channel and displace the peripheral zone outward. The amount of enlargement does not perfectly predict urinary symptoms: tissue configuration, smooth-muscle tone, bladder contractility and median-lobe protrusion also matter. See the focused guide to the transition zone and BPH growth.
What is the central zone?
The central zone is a cone- or wedge-shaped glandular region at the prostate base. It surrounds the ejaculatory ducts as they travel from the seminal vesicle/vas deferens junction toward the prostatic urethra. In a young gland it represents about 20–25% of glandular tissue.
The central zone is anatomically different from the “central gland” used in some radiology descriptions. Central gland is a practical imaging term that may group central and transition-zone tissues together; central zone is one specific anatomical zone. Cancers can arise here, but this is much less common than peripheral- or transition-zone origin.
What is the anterior fibromuscular stroma?
The anterior fibromuscular stroma is a band of smooth muscle and fibrous tissue over the front of the prostate. Unlike the three glandular zones, it contains little or no glandular tissue and does not produce prostatic secretions. It is continuous superiorly with bladder muscle and inferiorly with tissues near the external sphincter.
Because it is nonglandular, it normally appears relatively dark on T2-weighted MRI. A lesion can extend into this region from adjacent tissue, so “nonglandular” does not mean clinically irrelevant.
How much of the prostate does each zone occupy?
How do the zones differ clinically?
| Region | Defining relationship | Approximate young-adult share | Major clinical association |
|---|---|---|---|
| Peripheral zone | Posterior and lateral; near rectum | ≈70% of glandular tissue | Origin of most prostate cancers; also affected by inflammation |
| Central zone | Surrounds ejaculatory ducts at base | ≈20–25% | Uncommon cancer origin; may resemble transition tissue on imaging |
| Transition zone | Surrounds proximal prostatic urethra | ≈5% | Principal origin of BPH; minority of cancers |
| Anterior fibromuscular stroma | Anterior muscle/fibrous band | Not part of glandular percentage | Structural support; possible extension route from adjacent lesions |
| Periurethral glands | Immediately around urethra | Small variable component | Can contribute to median-lobe enlargement |
Are prostate zones the same as prostate lobes?
No. Lobes are an older gross-anatomy description—anterior, posterior, median and paired lateral lobes. Zones are based on ductal anatomy, tissue organization and disease behavior. The two systems overlap imperfectly, so “median lobe” should not be treated as a synonym for transition zone.
The prostatic urethra is the most useful landmark for understanding the transition and periurethral regions, while the ejaculatory ducts define the central zone. MRI and pathology reports generally favor zonal terminology because it communicates lesion location more consistently.
How are zones recognized on MRI?
Multiparametric MRI evaluates the prostate in axial, sagittal and coronal planes. The normal peripheral zone is often relatively bright on T2-weighted imaging, while the transition zone becomes heterogeneous and nodular with BPH. The anterior fibromuscular stroma is usually T2 dark because it is muscle- and fiber-rich.
PI-RADS uses different dominant MRI sequences when assessing peripheral-zone and transition-zone lesions. A signal abnormality is not a diagnosis: interpretation also considers diffusion, apparent diffusion coefficient, T2 morphology, enhancement, lesion size and evidence of extension. MRI findings must be integrated with PSA, examination, clinical risk and—when indicated—histology.
Summary
The prostate contains three glandular zones and one major nonglandular region. The peripheral zone forms most of the posterior/lateral gland and is the origin of most prostate cancers. The transition zone surrounds the proximal urethra and is the principal site of BPH. The central zone encloses the ejaculatory ducts, while the anterior fibromuscular stroma provides a nonglandular muscular-fibrous front surface. This zonal map complements the broader prostate anatomy and function hub and prevents inaccurate one-size-fits-all explanations of prostate disease.
Educational information only. Imaging, PSA values and urinary symptoms require interpretation by a qualified clinician.
Sources and evidence
- Endotext: Benign Prostate Disorders — McNeal zones, proportions and BPH relationships.
- NCI SEER Training: Prostate Anatomy — official zonal definitions.
- Normal 3T MR Anatomy of the Prostate and Surrounding Structures — MRI appearance and zone boundaries.
- Anatomic Imaging of the Prostate — transition and central-zone anatomy.
- MR Imaging of Prostate Zonal Anatomy — radiologic review of the McNeal model.


