
Prostate anatomy · Evidence-based patient education · Updated August 26, 2026
Where Is the Prostate Located? Relation to the Bladder, Urethra and Rectum
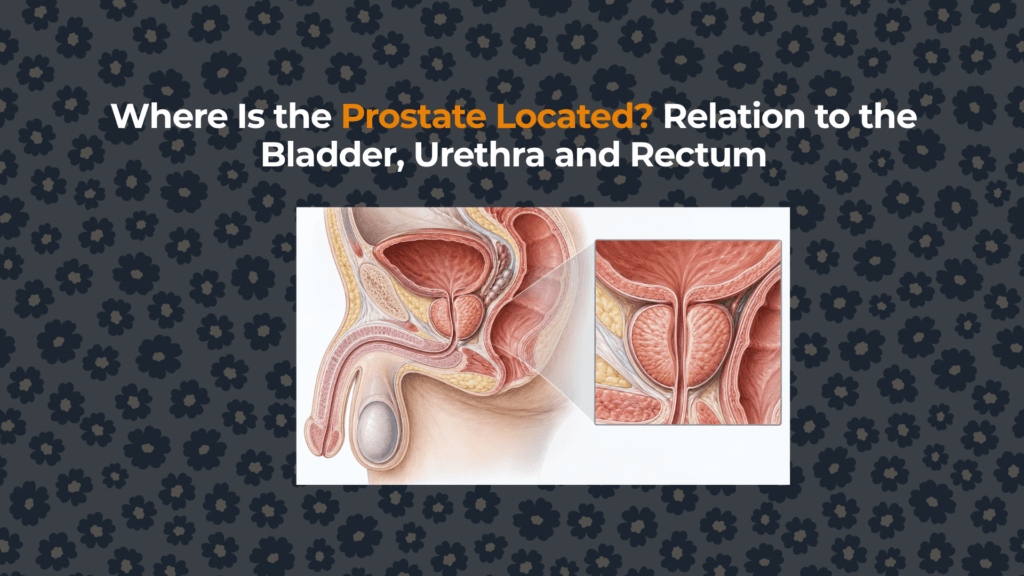
The prostate is a gland in the lower male pelvis. Its position at the junction of the urinary and reproductive tracts explains why prostate enlargement can affect urination, why part of the gland is reachable through the rectum and why prostate treatment can involve urinary and sexual structures.
Where is the prostate within the male pelvis?
The prostate occupies the lesser pelvis between the bladder and the pelvic floor. It is not inside the penis or abdomen, although the urethral channel connects it to both the bladder above and the penis below. In standard anatomical position, “anterior” means toward the pubic bone and “posterior” means toward the rectum.
| Reference structure | Relationship to the prostate | Why it matters |
|---|---|---|
| Urinary bladder | The prostate base is continuous with the bladder neck. | Growth near the outlet can increase resistance to urine flow. |
| Prostatic urethra | Runs from the bladder neck through the prostate. | Periurethral or transition-zone enlargement can narrow the outlet. |
| Rectum | Immediately posterior, separated by fascial tissue. | The posterior surface can be palpated during a digital rectal examination. |
| Pubic symphysis | Anterior to the prostate. | Defines the front of the retropubic surgical space. |
| Pelvic floor and external sphincter | Near the prostate apex and membranous urethra. | Relevant to continence-preserving surgery. |
| Seminal vesicles | Posterior-superior to the prostate base. | Their ducts join the vas deferens; ejaculatory ducts then traverse the prostate. |
How does the prostate relate to the bladder and urethra?
The bladder neck rests on the prostate base. From the internal urethral opening, the urethra descends through the gland as the prostatic urethra, continues as the short membranous urethra below the apex and then becomes the penile urethra. This continuous route is mapped in the existing guide to the urethra’s path from the bladder through the prostate and penis.
This does not mean the entire prostate squeezes the urethra uniformly. Benign prostatic hyperplasia usually arises in transition and periurethral tissue. The degree of urinary obstruction depends on tissue configuration, smooth-muscle tone, bladder function and outlet geometry—not prostate volume alone. A weak stream, hesitancy or retention therefore requires clinical evaluation rather than self-diagnosis from gland size.
Why can the prostate be examined through the rectum?
The rectal wall lies directly behind the prostate. During a digital rectal examination, a clinician inserts a lubricated, gloved finger into the rectum and palpates the accessible posterior surface through the intervening rectal wall and fascia. The examination can assess approximate size, symmetry, consistency, tenderness and palpable nodules, but it cannot feel every part of the gland or rule cancer in or out by itself.
This posterior relationship also explains why transrectal ultrasonography can image the prostate at close range. MRI, however, provides broader multiplanar assessment of zones, capsule, seminal vesicles and surrounding tissues. The anatomical proximity does not mean rectal symptoms are automatically caused by the prostate.
What lies above, behind and beside the prostate?
Seminal vesicles and ejaculatory ducts
The paired seminal vesicles lie behind the bladder and above the posterior prostate. Each seminal vesicle duct joins the corresponding vas deferens to form an ejaculatory duct. Those ducts pass through the prostate and open into the prostatic urethra. Downstream, semen continues through the same urethral route that later passes within the corpus spongiosum–urethra relationship in the penis.
Neurovascular bundles and pelvic sidewalls
Neurovascular bundles run posterolaterally beside the prostate. They contain autonomic nerves involved in erectile function and vessels supplying pelvic tissues. Their exact microscopic course varies, which is clinically important during prostate surgery. “Nerve-sparing” is an operative strategy, not a guarantee of unchanged erections or continence.
Prostate apex, membranous urethra and pelvic floor
The apex points inferiorly toward the membranous urethra and external urethral sphincter. This distal relationship helps explain why surgical planning must balance cancer control with preservation of continence structures. The pelvic floor also participates in urinary control and sexual mechanics; FBU’s anatomy of the penile root and pelvic attachments follows these structures farther forward and downward.
Does the prostate move or change position?
The gland is supported by fascial and ligamentous attachments, but the pelvic organs are not rigidly fixed. Bladder filling, rectal contents, body position and age-related tissue changes can slightly alter their shape and spatial relationship. Imaging protocols therefore standardize patient preparation and planes of measurement. The prostate also varies substantially between individuals, so “walnut-sized” is a teaching analogy, not a measurement.
Typical descriptions place a healthy adult prostate near 20–30 mL, but volume estimates depend on imaging method and the dimensions entered into the ellipsoid formula. Size alone does not establish obstruction, prostatitis or cancer. The broader FactBasedUrology Knowledge Hub explains how anatomical findings fit with symptoms, tests and clinical uncertainty.
What does prostate location explain clinically?
| Anatomical relationship | Clinical implication | What it does not prove |
|---|---|---|
| Around the proximal urethra | Prostate growth can contribute to bladder-outlet obstruction. | That every urinary symptom is caused by BPH. |
| Immediately anterior to rectum | Posterior gland is accessible to DRE and transrectal ultrasound. | That a normal DRE excludes clinically significant cancer. |
| Base at bladder neck | Treatment may affect bladder-outlet mechanics. | That gland size predicts symptom severity. |
| Apex near external sphincter | Relevant to continence-preserving dissection. | That continence outcomes can be guaranteed. |
| Posterolateral neurovascular bundles | Relevant to erectile-function preservation. | That all nerves are visible or safely separable. |
Summary
The prostate sits below the bladder, in front of the rectum and behind the pubic symphysis. It surrounds the prostatic urethra, meets the bladder neck at its base and approaches the pelvic floor and external sphincter at its apex. Seminal vesicles are posterior-superior, while neurovascular structures run posterolaterally. These relationships explain urinary obstruction, rectal examination, imaging access and the functional risks that clinicians consider during prostate treatment.
This article provides general medical education and cannot diagnose the cause of urinary, pelvic or sexual symptoms.
Sources and evidence
- NCBI Bookshelf: Transrectal Ultrasonography and Image-Guided Biopsies of the Prostate — spatial relations, measurements and imaging anatomy.
- National Cancer Institute SEER Training: Prostate Anatomy — base, apex, bladder, rectum and urethral relationships.
- Anatomy and Histology of the Human and Murine Prostate — human prostate location, normal weight and zonal anatomy.
- NCBI Bookshelf: Male Genitourinary Tract — urethral segments and ejaculatory pathway.


