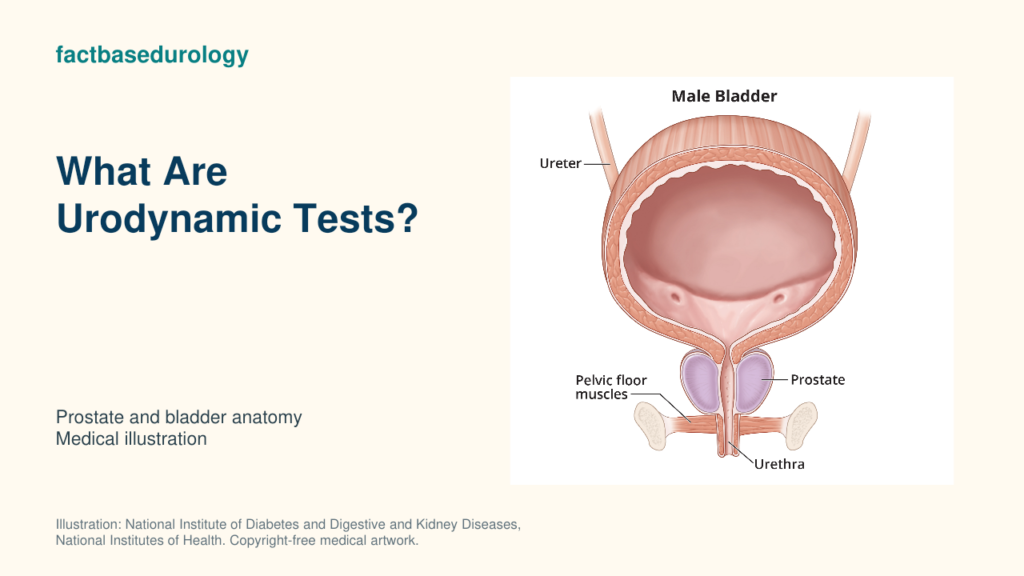
Urodynamics is a group of tests that measures how the bladder stores and releases urine. In men being evaluated for possible prostate-related obstruction, pressure-flow testing can distinguish increased outlet resistance from reduced bladder-muscle contraction.

01. Urodynamics: Measurement, Calculation and Interpretation
Urodynamic tests measure bladder storage and emptying; pressure-flow studies measure detrusor pressure and urine flow together to assess outlet resistance and contraction.
How are urodynamic tests measured or calculated?
Urodynamic testing records flow and pressures; detrusor pressure is calculated by subtracting abdominal pressure from bladder pressure during filling and voiding. Free uroflowmetry records flow without a catheter. Cystometry fills the bladder through a small catheter while measuring bladder and abdominal pressure. A pressure-flow study continues measurements during urination. Detrusor pressure is calculated by subtracting abdominal pressure from pressure measured inside the bladder.
Sensors record first sensation, urgency, capacity, involuntary contractions, detrusor pressure, flow and residual urine. Because catheters and the laboratory setting can change voiding, the clinician checks signal quality and whether the measured void resembles usual urination.
Which units, thresholds or scoring rules are used for urodynamics?
Urodynamics reports pressure in centimetres of water and flow in millilitres per second; BOOI and BCI combine pressure and flow to describe obstruction and contractility.
| Measure | Unit or calculation | Interpretive role |
|---|---|---|
| Detrusor pressure at Qmax | cm H₂O | Bladder-generated pressure at maximum flow. |
| Qmax | mL/s | Peak urine flow during the pressure-flow study. |
| BOOI | pdetQmax − 2(Qmax) | >40 obstructed; 20–40 equivocal; <20 unobstructed. |
| BCI | pdetQmax + 5(Qmax) | >150 strong; 100–150 normal; <100 weak contractility. |
Indices summarize physiology but do not replace trace quality, symptoms or clinical judgment. Thresholds describe urodynamic classifications, not histologic BPH or prostate size.
02. What Do Urodynamic Tests Measure?
Urodynamic tests assess bladder sensation, capacity, storage pressures, involuntary contractions and voiding function according to the tests performed.
What does a higher or lower urodynamic value mean?
Urodynamic high-pressure, low-flow voiding supports outlet obstruction; low-pressure, low-flow voiding supports weak contraction, subject to trace quality and clinical context. Involuntary pressure rises during filling indicate detrusor overactivity; reduced compliance means pressure rises disproportionately as the bladder fills. Capacity, sensation and residual urine add different information and should not be collapsed into one “normal” result.
Which factors can change or distort urodynamic testing?
Urodynamic results change with catheter position, calibration, movement, straining and filling rate; technical artefacts can mimic abnormal physiology. Anxiety, pain, infection and an unfamiliar voiding position can also change bladder behaviour. Interpretation requires technically valid traces and documentation of whether symptoms were reproduced.
03. Urodynamics: Reference Values, Modifiers and Limitations
Urodynamic reference indices support interpretation of pressure and flow; their categories require representative traces and the patient’s clinical context.
How should urodynamics be interpreted alongside other prostate findings?
Urodynamics complements prostate anatomy, symptoms, urinalysis, free flow and PVR by assessing functional mechanisms that anatomical measurements cannot establish.
Pressure-flow results explain mechanism and should be read with symptom burden, urinalysis, free-flow Qmax, PVR, prostate anatomy and treatment goals. A large prostate can exist without urodynamic obstruction; obstruction can exist with a preserved free-flow rate; and detrusor underactivity can coexist with obstruction.
What can urodynamics not diagnose or prove by itself?
Urodynamics cannot diagnose microscopic BPH or determine whether prostate tissue is benign or malignant; it evaluates urinary function.
04. How Does Urodynamics Affect the Next Clinical Decision?
Urodynamics guides selected BPH decisions by distinguishing outlet obstruction from weak bladder contraction when the distinction would change invasive treatment.
When should urodynamics be repeated, confirmed or combined with another test?
Urodynamics is repeated when traces are unreliable, expected symptoms were not reproduced or discordant findings would change a treatment decision. It is commonly combined with urinalysis, uroflowmetry and PVR; cystoscopy or imaging is added only for a separate anatomic question. Video-urodynamics is reserved for selected complex cases.
How does urodynamics change the next step in BPH?
Urodynamic obstruction supports consideration of outlet-relieving BPH treatment; predominant bladder weakness changes expected benefit and the discussion of alternatives. Detrusor underactivity may change expectations because reducing resistance does not directly restore bladder contractility. The EAU recommends selective—not routine—urodynamics before invasive treatment when the underlying mechanism remains uncertain or results would change the decision.
The UPSTREAM randomized trial included 820 men. At 18 months, adding routine urodynamics produced non-inferior symptom scores but did not reduce surgery: 38% underwent surgery in the urodynamics group versus 36% with routine care. These results support selective testing rather than testing every uncomplicated patient. UPSTREAM trial report.
Summary
- Urodynamics measures pressure, flow, storage and emptying.
- Pressure-flow testing can distinguish outlet obstruction from weak bladder contraction.
- Technical artefacts and an atypical laboratory void can distort results.
- The test is most valuable when its mechanism-level answer would change treatment.
Educational disclaimer: This article provides general medical education and cannot diagnose an individual condition or replace assessment by a qualified clinician.
Watch: How BPH is diagnosed
Urodynamics assesses bladder pressure and flow within BPH evaluation. FactBasedUrology explains how symptoms, examination and selected tests contribute to the broader diagnostic process in this video.