Uroflowmetry is a non-invasive test that records how quickly and in what pattern urine leaves the body. It converts one ordinary void into an objective flow curve, but the curve must be interpreted with voided volume, symptoms and post-void bladder volume.

01. Uroflowmetry: Measurement, Calculation and Interpretation
Uroflowmetry records urine flow over time and reports maximum flow, voided volume and curve shape; these findings describe flow without establishing its cause.
How is uroflowmetry measured or calculated?
Uroflowmetry measures a voluntary void into a flow-recording device, which calculates flow rate and plots the pattern over time. The machine repeatedly measures the weight or volume of collected urine and calculates millilitres per second throughout the void. It then plots a flow-versus-time curve. No catheter is required for free uroflowmetry.
The patient should have a comfortably full bladder and void in a usual position without straining. Immediately recording whether the void felt typical matters: an unfamiliar setting, urgency, abdominal pushing or deliberate interruption can alter the curve.
Which units, thresholds or scoring rules are used for uroflowmetry?
Uroflowmetry reports flow in millilitres per second and voided volume in millilitres; Qmax thresholds change the probability of obstruction rather than prove it.
| Output | Unit | Clinical role |
|---|---|---|
| Qmax | mL/s | Highest recorded flow; depends strongly on voided volume and effort. |
| Average flow | mL/s | Total voided volume divided by flow time. |
| Voided volume | mL | Shows whether the bladder was sufficiently filled for interpretation. |
| Flow/voiding time | seconds | Describes duration and interruptions. |
| Curve shape | visual pattern | A smooth bell-shaped curve is typical; flattened, intermittent or prolonged patterns require context. |
The EAU advises interpreting uroflowmetry with a bladder volume above 150 mL where possible. Its example thresholds show the trade-off: Qmax 10 mL/s had 70% specificity but 47% sensitivity for obstruction; Qmax 15 mL/s had 38% specificity and 82% sensitivity. These are probability shifts, not diagnostic cut-offs.
02. What Does Uroflowmetry Measure?
Uroflowmetry measures the amount and speed of urine passed during one void, including peak flow and the shape of the flow curve.
What does a higher or lower uroflowmetry value mean?
Lower uroflowmetry values suggest reduced flow but can reflect obstruction, weak bladder contraction or low voided volume; higher flow does not exclude obstruction. A lower Qmax indicates slower flow, but three common mechanisms overlap: bladder outlet obstruction, detrusor underactivity and inadequate bladder filling. Even Qmax above 15 mL/s cannot exclude obstruction because a compensated bladder may generate enough pressure to maintain flow.
The next page explains Qmax and maximum urinary flow rate in detail. On this page, the important point is that uroflowmetry is the complete test; Qmax is only one output.
Which factors can change or distort uroflowmetry?
Uroflowmetry changes with voided volume, bladder contraction, outlet relaxation, abdominal effort and whether the void represents the patient’s usual pattern.
| Factor | How it changes the result | Response |
|---|---|---|
| Voided volume below 150 mL | May produce an artificially low or poorly representative Qmax. | Repeat with a comfortably fuller bladder. |
| Urgency or overfilling | Can change bladder contraction and curve shape. | Interpret with bladder sensation and volume. |
| Straining or interrupted void | Creates spikes, pauses or an atypical pattern. | Record the event and repeat if necessary. |
| Medication, pain or anxiety | May alter outlet tone or the ability to void normally. | Review conditions at the time of testing. |
| Device artefact | Movement or stream missing the collector can distort the trace. | Check the raw curve before accepting summary numbers. |
03. Uroflowmetry: Reference Values, Modifiers and Limitations
Uroflowmetry thresholds require adequate volume and representative flow; pressure-flow testing resolves selected cases where the mechanism affects treatment.
How should uroflowmetry be interpreted alongside other prostate findings?
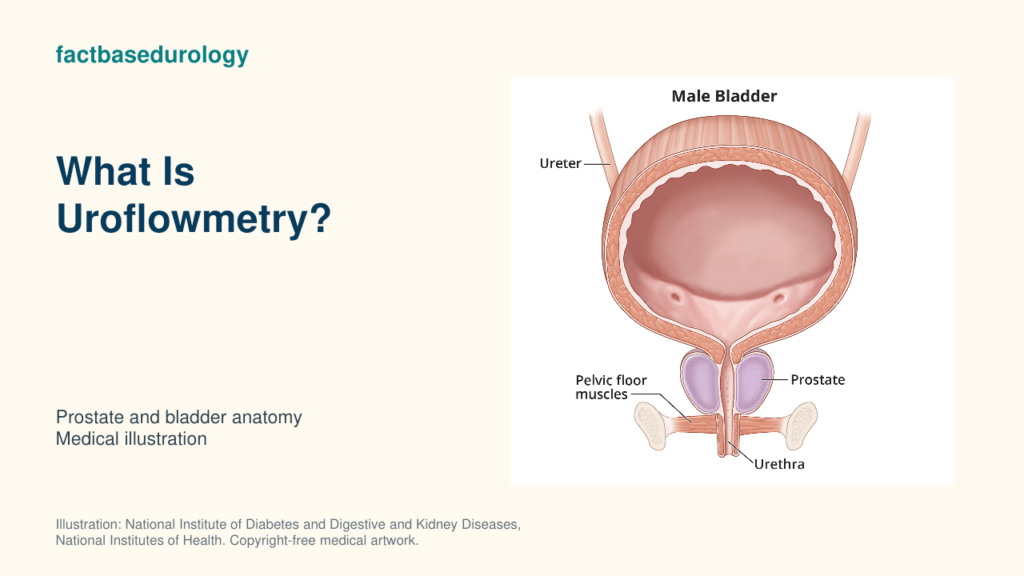
Uroflowmetry complements prostate anatomy, symptoms and PVR; the combined findings distinguish symptom burden, gland size, flow pattern and emptying. Prostate size can inform treatment selection but does not determine flow: a large prostate may not obstruct, and poor flow may occur without enlargement. Repeated similar curves carry more weight than a single atypical void.
What can uroflowmetry not diagnose or prove by itself?
Uroflowmetry cannot diagnose microscopic BPH or distinguish prostate obstruction from weak bladder contraction without additional assessment.
04. How Does Uroflowmetry Affect the Next Clinical Decision?
Uroflowmetry directs further evaluation when low or abnormal flow persists; the next test depends on residual urine, anatomy and whether mechanism changes treatment.
When should uroflowmetry be repeated, confirmed or combined with another test?
Uroflowmetry is repeated when voided volume is below 150 mL, the curve is abnormal or the patient reports an unrepresentative void. Pair it with a prompt PVR measurement to distinguish slow flow with effective emptying from slow flow with substantial residual urine. Selective urodynamics is considered when uncertainty between obstruction and weak contraction would change an invasive treatment decision.
How does uroflowmetry change the next step in BPH?
Persistent low uroflowmetry results prompt assessment of outlet resistance and bladder function before BPH treatment; a single low flow value does not establish obstruction. Uroflowmetry is recommended by the EAU before medical or invasive treatment, but the treatment choice still depends on the complete clinical profile.
Summary
- Uroflowmetry records flow rate, volume, time and curve shape during urination.
- Qmax is useful but varies with bladder filling and cannot diagnose obstruction alone.
- Low flow may reflect obstruction, weak bladder contraction or an unrepresentative void.
- Repeat abnormal or low-volume tests and interpret them with PVR and the wider evaluation.
Educational disclaimer: This article provides general medical education and cannot diagnose an individual condition or replace assessment by a qualified clinician.
Watch: How BPH is diagnosed
Uroflowmetry records urinary flow within BPH evaluation. FactBasedUrology explains how symptoms, examination and selected tests contribute to the broader diagnostic process in this video.