
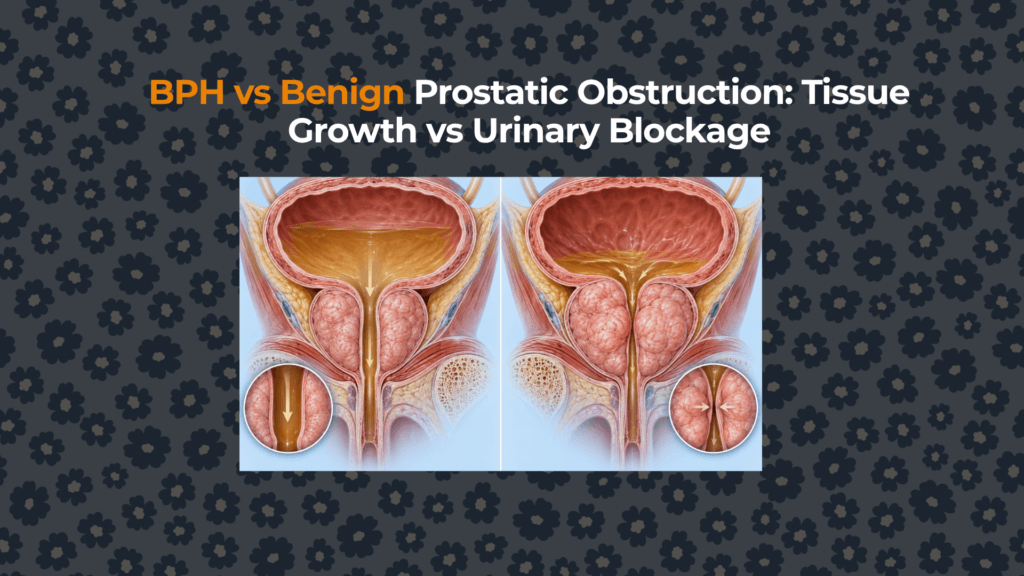
BPH vs Benign Prostatic Obstruction: Tissue Growth vs Urinary Blockage
BPH describes what prostate tissue is doing. Benign prostatic obstruction describes what the bladder outlet is doing.
01. What is the exact difference between BPH and BPO?
| Attribute | BPH | BPO |
|---|---|---|
| Entity | Tissue process | Functional outlet state |
| Definition | Benign stromal/glandular hyperplasia | Prostate-attributed resistance to bladder emptying |
| Reference evidence | Histology | Pressure–flow relationship, interpreted clinically |
| Typical measurement | Microscopic pattern | Detrusor pressure at maximum flow plus Qmax |
| Can exist without the other? | Yes | Yes; obstruction can have non-BPH causes |
The BPH clinical hub maps the full pathway. This article owns the obstruction claim.
02. BPO Is More Specific Than Bladder Outlet Obstruction
Bladder outlet obstruction (BOO) names resistance at the outlet without specifying the cause. Benign prostatic obstruction is BOO attributed to benign prostate anatomy or tone. Other causes include urethral stricture, bladder-neck dysfunction and, less commonly, malignancy. Calling every low-flow result “BPO” skips the causal step. The prostatic-urethra anatomy shows where gland geometry can change the outlet.
03. How does pressure–flow testing demonstrate obstruction?
During voiding, urodynamics records bladder detrusor pressure and urinary flow simultaneously. Obstruction typically produces relatively high detrusor pressure with low flow; detrusor underactivity can produce low pressure and low flow. Free uroflowmetry sees only the flow half of this relationship.
In the Abrams–Griffiths/ICS classification for men, a bladder outlet obstruction index (BOOI) above 40 is obstructed, 20–40 is equivocal, and below 20 is unobstructed. PdetQmax is detrusor pressure in cmH₂O at maximum flow; Qmax is maximum flow in mL/s. These categories classify a test under standardized conditions—they do not independently name the anatomical cause.
04. Low Maximum Flow Is a Screening Signal, Not Proof
Qmax depends on outlet resistance, bladder contractility and voided volume. In the ICS “BPH” study, a Qmax cutoff of 10 mL/s had 47% sensitivity, 70% specificity and 70% positive predictive value for BOO in the studied men. Raising the cutoff to 15 mL/s increased sensitivity to 82% but reduced specificity to 38%. A single threshold therefore trades missed obstruction against false attribution.
05. Does High Post-Void Residual Mean BPO?
No. Residual urine may result from obstruction, weak detrusor contraction or both. EAU evidence reports that a 50 mL residual threshold had only 63% positive predictive value and 52% negative predictive value for BOO. Residual volume is clinically useful for emptying efficiency and longitudinal risk, but it cannot identify the mechanism alone.
06. Prostate Size and BPH Histology Cannot Confirm BPO
A large transition zone or median lobe increases the probability of prostate-related resistance, yet outward growth may have little outlet effect. Conversely, a modest gland with intravesical protrusion may distort the bladder neck. Histologic BPH confirms benign cell proliferation; it does not measure pressure, flow or bladder adaptation.
The prior BPH-versus-enlargement comparison owns the tissue-versus-size boundary.
07. Can Severe LUTS Occur Without Obstruction?
Yes. Symptom scores quantify storage, voiding and post-micturition burden but do not identify cause. Detrusor overactivity, nocturnal polyuria, infection, medications, neurologic disease and impaired contractility can produce similar complaints. The reverse is also possible: objective obstruction may be present with limited bother. The size–symptom comparison separates gland volume from symptom severity.
For the wider differential, continue to the male urinary health hub.
08. Four Clinical Patterns Require Different Reasoning
09. When is invasive urodynamics useful?
Pressure–flow testing is not required for every man with uncomplicated LUTS. It becomes more valuable when the mechanism is uncertain and the answer could change invasive treatment—such as suspected detrusor underactivity, discordant symptoms and flow, previous unsuccessful surgery, neurologic disease or selected preoperative decisions. EAU recommendations emphasize individual indications rather than routine use.
How should BPH and BPO be documented?
Document the observed level: histologic BPH, measured enlargement, LUTS phenotype, low flow, elevated residual, suspected BPO or pressure–flow-confirmed obstruction. Avoid moving from one level to another without evidence. Treatment should target the demonstrated mechanism and the outcome important to the patient.


