
What Is a Normal Prostate Size? Volume, Age and Measurement Ranges
“Normal prostate size” is not one number. It is a reference distribution shaped by age, population, gland zone and measurement method.
01. What does “normal prostate size” actually mean?
Normal size means a value observed within a reference population, not a line separating health from disease. A measurement becomes interpretable only after identifying the person’s age, the imaging method, whether total or zonal volume was measured, and why the scan was performed.
The separate prostate-volume guide explains how imaging measurements become an estimated volume. This page stays focused on interpreting the resulting number.
02. What size is commonly reported for a healthy young-adult prostate?
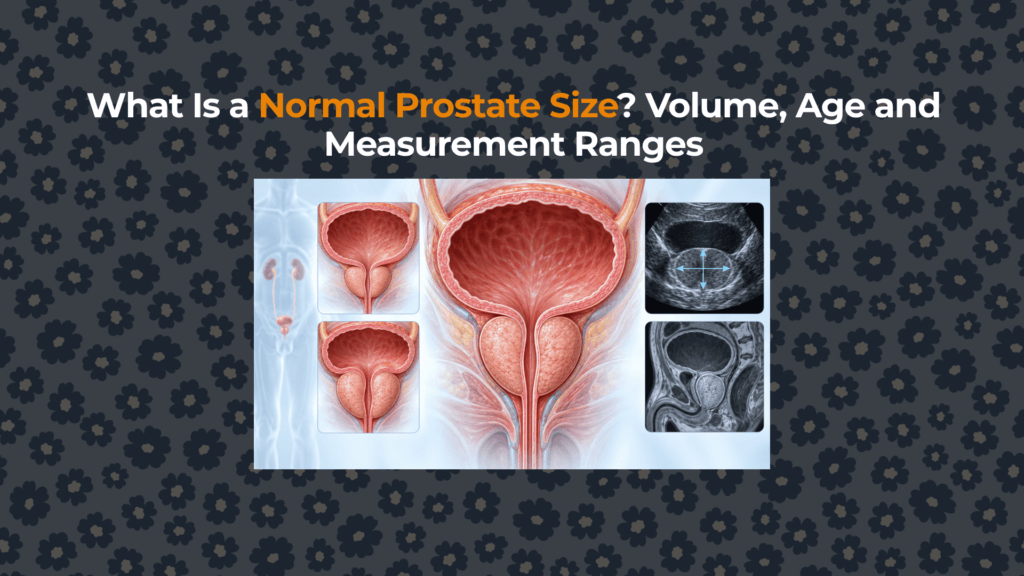
An ultrasound review describes a normal prostate as approximately 3 × 3 × 5 cm, or about 25 mL. Ultrasound standards report average healthy-young-adult dimensions near 3.75–4.0 × 2.5–3.0 × 3.1–3.8 cm and a volume around 20–25 cm³.
These values are useful orientation points, but their apparent precision should not be overstated. They come from reviews and standards that summarize particular populations and methods. They are not universal percentile limits for every adult.
03. How does normal prostate size change with age?
Population distributions shift upward with age, but they continue to overlap. A gland of 30 mL can be above one young-adult reference while remaining common in an older population. Conversely, age does not guarantee enlargement.
Longitudinal studies are required to describe personal growth. Cross-sectional studies only compare different people at different ages. The age-related prostate-change article explains why the reported mean growth near 1.6% per year cannot be applied as an individual rule.
04. Which prostate zone drives most age-related size increase?
Later-life enlargement is usually driven by the transition and central-gland region rather than uniform expansion of every zone. In an MRI study of 503 men, age correlated positively with whole-prostate and central-gland volumes, while peripheral-zone volume showed no significant age correlation.
The cohort consisted of men who underwent MRI before prostate-cancer treatment, so the findings describe a selected clinical population. Still, they demonstrate why a single total-volume number can hide different internal anatomy. The transition-zone guide maps the tissue most associated with BPH growth.
05. Why can ultrasound and MRI report different prostate sizes?
Imaging does not place the physical gland on a measuring tray. A reader selects boundaries and axes from images, then applies a formula or segmentation method. Probe angle, bladder filling, gland shape and whether a median lobe is included can change the estimate.
EAU evidence notes that, in one 640-man series, TRUS volumes averaged 8% smaller than MRI. Another cited study found transabdominal ultrasound overestimated volume by 9.9 mL. Those are study results—not correction factors that should be applied to every report.
06. Does a prostate above 25 or 30 mL mean BPH?
No. A volume above a young-adult reference means the gland is larger than that reference—not that tissue has been examined histologically. EAU terminology reserves BPH for the characteristic benign histologic pattern, while enlargement is an anatomical state.
| Finding | What it establishes | What it cannot establish alone |
|---|---|---|
| Volume above a reference | A larger imaging estimate relative to that reference | Histologic BPH, obstruction or symptom cause |
| Histologic BPH | Benign stromal and epithelial hyperplasia | That the gland is large or symptomatic |
| Male LUTS | Storage, voiding or post-micturition complaints | That the prostate is responsible |
| Benign prostatic obstruction | Outlet resistance attributed to the prostate | That volume must exceed one cutoff |
The BPH-versus-enlargement comparison resolves this terminology directly.
07. Can a normal-size prostate still cause urinary symptoms?
Yes. Symptoms can arise from outlet geometry, dynamic smooth-muscle tone, bladder overactivity, weak detrusor contraction, nocturnal urine production, urethral narrowing, infection, neurologic disease or medicines. A modest gland with median-lobe protrusion may affect the outlet differently from a larger gland that expands outward.
This is why prostate size and symptom severity must remain separate clinical variables. Volume predicts some group-level progression risks, but it is not a symptom score.
08. When does prostate size become clinically useful?
Size becomes useful when it changes interpretation or management. It can contribute to PSA-density calculation, progression-risk estimation, medicine selection and procedure planning. In EAU guidance, volume above 40 mL is one example of increased progression risk used when considering long-term 5-alpha-reductase inhibitor therapy for moderate-to-severe LUTS.
That value is a treatment-context example—not a universal definition of enlargement and not an instruction to treat every gland above 40 mL.
| Clinical use | Why volume matters | Required companion information |
|---|---|---|
| Compare over time | May identify a meaningful trajectory | Comparable modality, planes and treatment status |
| PSA density | Volume is the denominator | PSA context, MRI findings and risk pathway |
| BPH medication | Larger glands may have different progression risk | Symptoms, contraindications and patient priorities |
| Procedure planning | Technique suitability can depend on size and shape | Median lobe, anatomy, goals and local expertise |
How should a prostate-size report be interpreted?
Read the report as a measurement record, not a verdict. Confirm the modality, dimensions, total versus zonal volume, formula or segmentation method, comparison date and reason for imaging. A small difference between two reports may be methodological rather than biological.
Summary
A commonly cited healthy young-adult prostate is approximately 20–25 mL, but “normal” is a reference distribution rather than one cutoff. Age shifts the distribution, central/transition-zone growth drives much of later enlargement, and ultrasound and MRI can disagree. The useful interpretation combines population, method, anatomy and clinical purpose—never volume alone.
Educational information only; individual measurements require qualified clinical interpretation.
Evidence sources
- Ultrasound of the prostate: anatomy and volume measurement.
- Standards of prostate ultrasound examination.
- Turkbey et al.: age-related zonal MRI volumes in 503 men.
- EAU: prostate-volume measurement and PSA-density evidence.
- EAU: male LUTS disease management.
- Population reference ranges for prostate volume and annual change.


