
Prostate anatomy · MRI and cancer context · Updated August 26, 2026
What Is the Prostate Peripheral Zone? Anatomy and Prostate Cancer Relevance
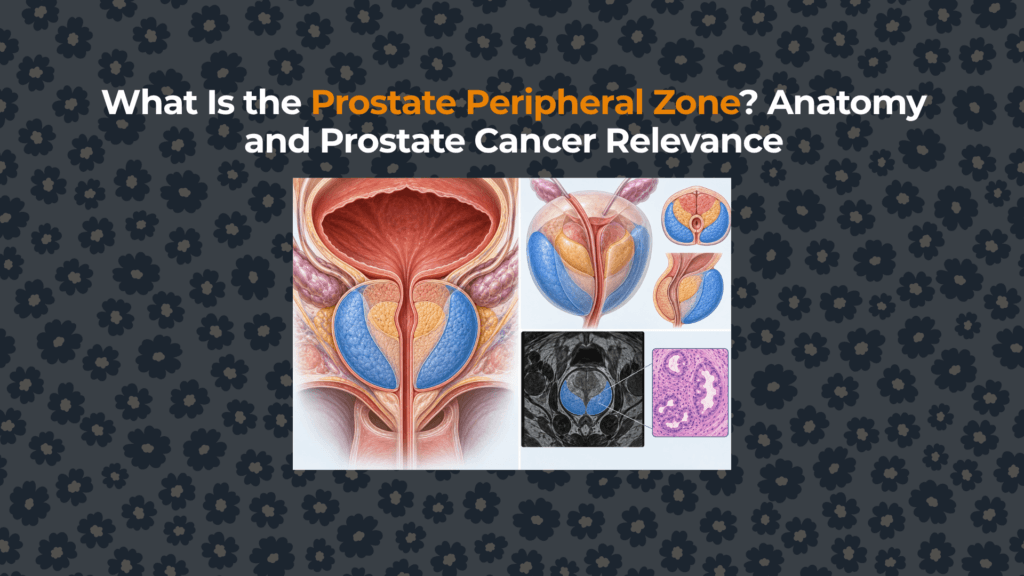
The peripheral zone is the largest glandular region of the prostate and occupies most of its posterior and lateral outer tissue. Its proximity to the rectum makes part of it palpable, and its tissue biology makes it the most frequent zone of origin for prostate cancer—but many peripheral-zone abnormalities are benign.
Where is the peripheral zone located?
The peripheral zone forms a broad outer shell around much of the central zone and extends posterolaterally from base to apex. Its relative volume increases toward the prostate apex. Posteriorly, it lies immediately in front of the rectum, separated by the prostate’s outer fibromuscular boundary and intervening fascial tissue.
That orientation is shown within the broader prostate zonal anatomy map. It also explains why clinicians can palpate part of the posterior gland during a rectal examination and why transrectal ultrasound provides close imaging access.
How much of the prostate is peripheral zone?
Classic anatomical sources place the peripheral zone near 70% of the glandular prostate in younger adults. That figure refers to glandular tissue, not necessarily 70% of every person’s total measured prostate volume. Age-related transition-zone enlargement can compress and displace peripheral tissue, changing the apparent proportions.
The peripheral zone contains many ducts and secretory acini with less densely interwoven smooth muscle than central tissues. This fluid-rich microarchitecture contributes to its relatively high signal on normal T2-weighted MRI.
Why do many prostate cancers arise in the peripheral zone?
Across anatomical, imaging and pathological literature, approximately 60–75% of prostate cancers are described as peripheral-zone in origin. The zone’s large volume of glandular epithelium contributes to the number of cells capable of forming adenocarcinoma, but volume alone does not fully explain zonal susceptibility.
A prevalence statement is not a diagnosis. Most men do not have cancer simply because the peripheral zone is large, and many MRI abnormalities in this region are benign. A focused prostate-cancer hub should integrate this anatomy with PSA, risk factors, MRI, biopsy grade and stage rather than treating location as fate.
What does the peripheral zone look like on MRI?
On high-quality T2-weighted MRI, normal peripheral-zone tissue is commonly homogeneous and relatively bright. Suspicious cancers may appear as focal low-signal areas, but T2 signal alone lacks adequate specificity. Post-biopsy hemorrhage, prostatitis, scarring, atrophy, treatment effects and calcification can also reduce signal.
In PI-RADS assessment, diffusion-weighted imaging is the dominant sequence for peripheral-zone lesions. Restricted water diffusion may create high signal on high-b-value diffusion images and low apparent diffusion coefficient, but even this pattern is not cancer-specific. Dynamic contrast enhancement can modify assessment in defined circumstances; it does not independently establish malignancy.
Can prostatitis affect the peripheral zone?
Yes. Acute or chronic inflammation can involve peripheral tissue and can cause pain, urinary symptoms, PSA elevation and MRI appearances that overlap with cancer. Inflammation can be diffuse, wedge-shaped or focal; no one MRI pattern rules prostatitis in or cancer out.
Prostatitis itself is a clinical category with infectious and noninfectious forms. Fever, chills, painful urination, severe pelvic pain or systemic illness requires timely assessment. The prostatitis and prostate-pain hub separates bacterial infection from chronic pelvic pain syndromes and other mimics.
Why can the peripheral zone be felt during DRE?
The posterior peripheral zone lies directly in front of the rectum. A clinician can therefore palpate part of the posterior surface through the rectal wall, assessing symmetry, consistency, tenderness and nodularity. The precise relationship between the prostate and rectum explains that access.
DRE cannot reach or characterize the entire prostate, and a normal examination does not exclude clinically significant cancer. Conversely, firmness, asymmetry or tenderness is not automatically malignant. DRE is one information source within a broader assessment.
Peripheral zone vs transition zone
| Attribute | Peripheral zone | Transition zone |
|---|---|---|
| Location | Posterior and posterolateral outer gland | Around proximal prostatic urethra |
| Young-adult glandular proportion | ≈70% | ≈5% |
| Main benign association | Inflammation, atrophy and other mimics | BPH nodular growth |
| Reported cancer-origin share | ≈60–75% | ≈20–30% |
| Dominant PI-RADS sequence | Diffusion-weighted imaging | T2-weighted morphology |
| Effect of BPH | May be compressed outward | May expand dramatically |
The complementary article on transition-zone anatomy and BPH growth explains why the smaller inner zone can dominate urinary-outlet geometry.
What does a peripheral-zone lesion mean?
It means imaging or examination identified an area that differs from surrounding peripheral tissue. It does not specify the cause. Clinicians combine lesion morphology and diffusion with PSA density, prior imaging, prior biopsy, risk history and examination to decide whether surveillance, repeat imaging or biopsy is appropriate.
| Finding | Possible explanations | Typical next-context question |
|---|---|---|
| Low T2 signal | Cancer, inflammation, hemorrhage, fibrosis, atrophy | What do diffusion and T1 images show? |
| Diffusion restriction | Hypercellular cancer or inflammatory/benign mimic | Is it focal, reproducible and morphologically suspicious? |
| Early enhancement | Increased vascularity from several causes | Does it correspond to a diffusion abnormality? |
| Palpable nodule | Malignancy, calcification, benign asymmetry or fibrosis | How does it relate to PSA, MRI and risk? |
| Tenderness | Inflammation or another pelvic pain source | Are infection signs or urinary findings present? |
Summary
The peripheral zone is the largest glandular zone, forming most of the posterior and lateral prostate and extending toward the apex. It is accessible in part through the rectum and is the origin of most prostate cancers reported in population series. Yet inflammation, hemorrhage, atrophy and fibrosis commonly mimic cancer. Peripheral-zone findings become medically meaningful only when MRI sequences, PSA context, examination, risk and—when needed—biopsy are interpreted together.
Educational information only; it cannot diagnose an individual prostate lesion.


